Erb-Duchenne Palsy (C5-C6)Upper Arm Birth Palsy (Waiter's Tip) (Erb-Duchenne Palsy (C5-C6))
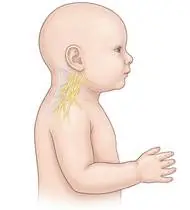
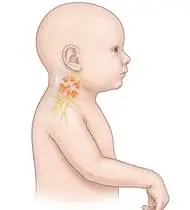
Erb-Duchenne Palsy (C5-C6) — Overview
Erb-Duchenne Palsy (Upper Trunk C5–C6 ± C7 Obstetric Palsy) accounts for ~75–80% of all birth brachial plexus injuries. Lesion at Erb's point (where C5 and C6 unite to form the upper trunk) denervates the suprascapular nerve (supraspinatus, infraspinatus), axillary nerve (deltoid, teres minor), and musculocutaneous nerve (biceps, brachialis)—plus the radial nerve (C7 triceps/wrist extensors) in extended Erb's palsy. Because the lower trunk (C8–T1) is spared, the extrinsic and intrinsic hand flexors remain strong (intact palmar grasp reflex!), while the paralyzed abductors, external rotators, elbow flexors, and supinators leave the arm in the classic 'Waiter's Tip Posture': shoulder adducted and internally rotated, elbow extended, forearm pronated, and wrist flexed.
Erb-Duchenne palsy (upper arm birth palsy / C5–C6 'Waiter's Tip' palsy) is the most common and most recoverable type of birth nerve injury. Because only the upper nerves (C5–C6) are stretched while the lower hand nerves (C8–T1) are completely healthy, your baby can already grasp your finger strongly with their hand, and physiotherapy focuses on waking up shoulder lifting, outward rotation, elbow bending (biceps), and turning the palm upward!
Primary Causes & Biomechanics
Key Points You Should Know
- •Traction on the C5–C6 upper trunk (most superficial and vulnerable roots) during delivery
- •Classic muscular imbalance: Paralyzed Supraspinatus/Infraspinatus/Deltoid/Biceps/Supinator vs. Unopposed Strong Subscapularis/Pectoralis Major/Pronator Teres, creating rapid internal rotation and pronation contractures
- •Ipsilateral Phrenic Nerve (C3–C5) injury in ~5% of cases causing diaphragmatic eventration/hemiparesis
- •Why Your Baby's Hand Grasp Is Already Strong: In Erb's palsy, the nerves to the fingers are intact! We use that strong hand grasp to hold light rattles while teaching the elbow (biceps) and shoulder to lift the toy to the mouth.
- •Undoing the 'Waiter's Tip' Position: Because the arm wants to turn inward with the palm facing back, play games where your child reaches for stickers, bubbles, or high-fives with their palm turned UP ('supination') and elbow tucked in.
- •Checking the Shoulder Blade During Stretches: Whenever you gently rotate your baby's arm outward, hold their shoulder blade gently against the mattress with your other hand so the true shoulder ball-and-socket stretches.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Active Movement Scale (AMS) specifically tracking Elbow Flexion (Biceps), Shoulder External Rotation (Infraspinatus), Shoulder Abduction (Deltoid/Supraspinatus), and Forearm Supination.
2. Special Clinical Provocation & Neurological/Functional Tests
Passive External Rotation in Adduction (with scapula stabilized — must remain >45°!), Cookie Test at 9 months, and Trumpet Sign evaluation.
3. Standardized Clinical Outcome Scales & Imaging Criteria
AMS (0–7), Mallet Classification (I–V), and Glenohumeral Ultrasound (alpha angle <30° confirms centered humeral head).
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7) moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Classic 'Waiter's Tip' Posture: The arm hangs at the side with the shoulder turned inward, elbow straight, forearm turned palm-backward, and wrist slightly curled—while the fingers curl and grasp normally.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Anti-'Waiter's Tip' Diaper-Change Mobilization Phase: At every diaper change (4–5x/day), perform scapula-stabilized passive external rotation, gentle elbow flexion/extension, forearm supination (turning palm to the sky!), and wrist extension (with a lightweight cock-up wrist splint if C7 wrist drop is present).
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7) without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in Erb-Duchenne Palsy (C5-C6).
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Biceps & Supinator Play Facilitation Phase: Side-lying hand-to-mouth play (placing soft teething toys or sweet drops on the baby's thumb/back of hand so they flex the elbow and supinate to bring it to the mouth!), gentle tactile brushing over the deltoid/biceps/extensors, and wand/assisted overhead reach.
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7).
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Phase 3 — Anti-Trumpet External Rotation & Quadruped Phase: Towel-supported external rotation play, reaching overhead for stickers/balloons with the thumb pointing up ('high-five / palm-up' games!), and supported quadruped weight-bearing to stabilize the winged scapula.
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •Why Your Baby's Hand Grasp Is Already Strong: In Erb's palsy, the nerves to the fingers are intact! We use that strong hand grasp to hold light rattles while teaching the elbow (biceps) and shoulder to lift the toy to the mouth.
- •Calm Protection & Gentle Start: During the initial stage of Upper Arm Birth Palsy (Waiter's Tip), avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Undoing the 'Waiter's Tip' Position: Because the arm wants to turn inward with the palm facing back, play games where your child reaches for stickers, bubbles, or high-fives with their palm turned UP ('supination') and elbow tucked in.
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Checking the Shoulder Blade During Stretches: Whenever you gently rotate your baby's arm outward, hold their shoulder blade gently against the mattress with your other hand so the true shoulder ball-and-socket stretches.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Towel-Supported Glenohumeral External Rotation (Infraspinatus & Teres Minor)
1. Outward Forearm Rotation with Rolled Towel Under Elbow
External rotation performed at 90° elbow flexion with a rolled towel placed between the elbow and trunk (20°–30° scaption). Enhances infraspinatus/teres minor recruitment while preventing superior humeral head migration and deltoid shear. Specifically indicated in Erb-Duchenne Palsy (C5-C6) rehabilitation to optimize upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7) biomechanics and neuromuscular control.
Place a small rolled towel between your elbow and your side with your elbow bent at 90 degrees. Keeping your elbow pressed gently against the towel, rotate your forearm outward, hold for 3 seconds, and return slowly. Perform smoothly within a comfortable, pain-free range to support your Upper Arm Birth Palsy (Waiter's Tip) recovery.
 🔍 Enlarge
2. Proximal & Distal Radioulnar Joint (PRUJ/DRUJ) Supination and Pronation
2. Elbow-at-Side Palm Up and Palm Down Rotation
Isolated forearm rotation with the elbow flexed at 90° and adducted against the trunk to eliminate compensatory glenohumeral rotation. Restores radial head spinning and distal radioulnar translation. Specifically indicated in Erb-Duchenne Palsy (C5-C6) rehabilitation to optimize upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7) biomechanics and neuromuscular control.
Keep your elbow bent at a right angle and tucked closely against your waist. Slowly turn your palm upward toward the ceiling, hold for 3 seconds, then turn your palm downward toward the floor. Perform smoothly within a comfortable, pain-free range to support your Upper Arm Birth Palsy (Waiter's Tip) recovery.
 🔍 Enlarge
3. Isolated Humeroulnar Active/Active-Assisted Flexion and Extension ROM
3. Full Elbow Bending and Straightening
Controlled full-arc elbow flexion and extension with the humerus stabilized in neutral alignment. Prevents anterior capsular contracture (extension loss) and restores biceps/triceps reciprocal excursion. Specifically indicated in Erb-Duchenne Palsy (C5-C6) rehabilitation to optimize upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7) biomechanics and neuromuscular control.
Keep your upper arm comfortably close to your body. Slowly bend your elbow to bring your hand toward your shoulder, hold for 3 seconds, then slowly straighten your elbow as far as comfortable. Perform smoothly within a comfortable, pain-free range to support your Upper Arm Birth Palsy (Waiter's Tip) recovery.
 🔍 Enlarge
4. Graduated Wall Finger-Walk (Spider Climb) Active-Assisted Elevation
4. Wall Finger-Climbing (Spider Walk) Exercise
Facing or standing perpendicular to a wall, walking the fingers progressively upward to achieve controlled active-assisted glenohumeral flexion/scaption while avoiding compensatory trunk lean or shoulder shrugging. Specifically indicated in Erb-Duchenne Palsy (C5-C6) rehabilitation to optimize upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7) biomechanics and neuromuscular control.
Stand facing a wall and gently walk your fingers up the wall like a spider as high as you comfortably can without shrugging your shoulder, hold for 5 seconds, and walk your fingers back down. Perform smoothly within a comfortable, pain-free range to support your Upper Arm Birth Palsy (Waiter's Tip) recovery.
 🔍 Enlarge
5. Supine Wand-Assisted (Cane) Active-Assisted Shoulder Elevation
5. Lying Cane/Stick-Assisted Two-Handed Arm Raise
In supine (scapula stabilized against the plinth and gravity eliminated in the final arc), the unaffected upper extremity guides a wand/stick to elevate the affected shoulder smoothly without deltoid-induced superior humeral shear. Specifically indicated in Erb-Duchenne Palsy (C5-C6) rehabilitation to optimize upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7) biomechanics and neuromuscular control.
Lie on your back holding a light stick or cane with both hands. Use your healthy arm to gently guide both arms up overhead as far as comfortable, hold for 3 seconds, and slowly lower. Perform smoothly within a comfortable, pain-free range to support your Upper Arm Birth Palsy (Waiter's Tip) recovery.
 🔍 Enlarge
6. Closed-Chain Wall Ball Stabilization & Serratus Anterior Protraction
6. Wall Ball Circles & Shoulder Blade Control
Rhythmic stabilization and small circular perturbations with the hand pressing a soft ball against the wall at shoulder height. Stimulates glenohumeral joint mechanoreceptors, serratus anterior upward rotation, and rotator cuff co-contraction. Specifically indicated in Erb-Duchenne Palsy (C5-C6) rehabilitation to optimize upper trunk of the brachial plexus (C5–C6 nerve roots / Erb's point, ± C7) biomechanics and neuromuscular control.
Hold a small soft ball against the wall at chest or shoulder height with your elbow nearly straight. Gently press into the ball and trace small, controlled clockwise and counterclockwise circles. Perform smoothly within a comfortable, pain-free range to support your Upper Arm Birth Palsy (Waiter's Tip) recovery.
Movements to Avoid & Strict Precautions
1. Lifting the Baby or Toddler by the Hands or Under the Armpits
1. Pulling the child up by their hands or lifting them under the armpits
2. Rotating the Forearm From the Wrist Instead of Holding Above the Wrist / Distal Forearm
2. Twisting the baby's hand at the wrist during supination stretches (always hold gently along the forearm!)
3. Allowing the Child to Eat and Play Using the 'Trumpet' High-Elbow Compensation Without Guidance
3. Letting the child hike their elbow up by their ear instead of guiding the elbow down and rotating the palm up
4. Skipping Daily Outward-Rotation Stretches Once the Arm Starts Moving
4. Stopping daily outward-rotation stretches just because the baby can lift the arm (internal tightness can still develop during growth!)
Erb-Duchenne Palsy (C5-C6) — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

Obstetric Brachial Plexus and Erb-Duchenne Palsy Clinical Exam and Overview
Erb-Duchenne Palsy (Upper Trunk C5–C6 ± C7 Obstetric Palsy) accounts for ~75–80% of all birth brachial plexus injuries. Lesion at Erb's point (where C5 and C6 unite to form the upper trunk) denervates the suprascapular nerve (supraspinatus, infraspinatus), axillary nerve (deltoid, teres minor), and musculocutaneous nerve (biceps, brachialis)—plus the radial nerve (C7 triceps/wrist extensors) in extended Erb's palsy. Because the lower trunk (C8–T1) is spared, the extrinsic and intrinsic hand flexors remain strong (intact palmar grasp reflex!), while the paralyzed abductors, external rotators, elbow flexors, and supinators leave the arm in the classic 'Waiter's Tip Posture': shoulder adducted and internally rotated, elbow extended, forearm pronated, and wrist flexed.
Erb-Duchenne palsy (upper arm birth palsy / C5–C6 'Waiter's Tip' palsy) is the most common and most recoverable type of birth nerve injury. Because only the upper nerves (C5–C6) are stretched while the lower hand nerves (C8–T1) are completely healthy, your baby can already grasp your finger strongly with their hand, and physiotherapy focuses on waking up shoulder lifting, outward rotation, elbow bending (biceps), and turning the palm upward!
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

Pediatric Brachial Plexus (Erb-Duchenne & Klumpke) Rehabilitation Exercises
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Anti-'Waiter's Tip' Diaper-Change Mobilization Phase: At every diaper change (4–5x/day), perform scapula-stabilized passive external rotation, gentle elbow flexion/extension, forearm supination (turning palm to the sky!), and wrist extension (with a lightweight cock-up wrist splint if C7 wrist drop is present).
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: Why Your Baby's Hand Grasp Is Already Strong: In Erb's palsy, the nerves to the fingers are intact! We use that strong hand grasp to hold light rattles while teaching the elbow (biceps) and shoulder to lift the toy to the mouth.

Upper Extremity Range of Motion Exercises in Brachial Plexus Injuries
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Biceps & Supinator Play Facilitation Phase: Side-lying hand-to-mouth play (placing soft teething toys or sweet drops on the baby's thumb/back of hand so they flex the elbow and supinate to bring it to the mouth!), gentle tactile brushing over the deltoid/biceps/extensors, and wand/assisted overhead reach.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Undoing the 'Waiter's Tip' Position: Because the arm wants to turn inward with the palm facing back, play games where your child reaches for stickers, bubbles, or high-fives with their palm turned UP ('supination') and elbow tucked in.
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

Obstetric Brachial Plexus and Erb-Duchenne Palsy Clinical Exam and Overview
Goniometric ROM & Postural / Kinematic Analysis: Active Movement Scale (AMS) specifically tracking Elbow Flexion (Biceps), Shoulder External Rotation (Infraspinatus), Shoulder Abduction (Deltoid/Supraspinatus), and Forearm Supination.
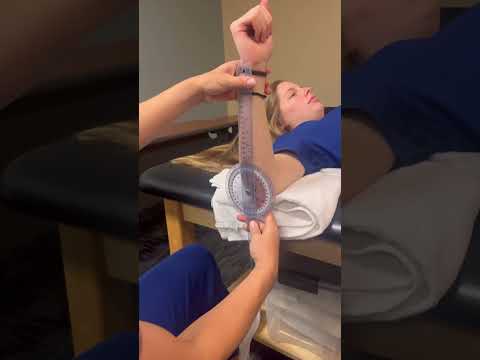
Shoulder Joint Goniometric Measurement (Flexion, Abduction, Internal & External Rotation)
Special Clinical Provocation & Neurological/Functional Tests: Passive External Rotation in Adduction (with scapula stabilized — must remain >45°!), Cookie Test at 9 months, and Trumpet Sign evaluation.