Dupuytren's Contracture (Palmar Fibromatosis)Palmar Fascia Thickening (Dupuytren's Contracture)
Dupuytren's Contracture (Palmar Fibromatosis) — Overview
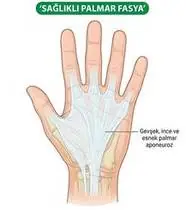
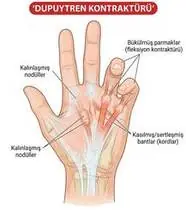
Dupuytren's contracture (palmar fascial fibromatosis) is a benign, progressive fibroproliferative disorder of the palmar aponeurosis in which fibroblasts differentiate into contractile myofibroblasts (producing excess Type III collagen via TGF-β signaling). It progresses from painless palmar nodules and skin pitting near the distal palmar crease to longitudinal fibrous cords that draw the ring (4th) and little (5th) fingers into progressive MCP and PIP flexion contracture.
Dupuytren's contracture (palmar fascia thickening) is a condition where the connective tissue layer just under the skin of your palm thickens into small firm knots (nodules) and cords that gradually pull the ring and little fingers inward so they cannot straighten completely.
Primary Causes & Biomechanics
Key Points You Should Know
- •Genetic predisposition (autosomal dominant with variable penetrance), older age, male sex, diabetes mellitus, smoking, and alcohol consumption
- •Transformation of normal pretendinous fascial bands into contractile myofibroblastic cords (sparing the underlying flexor tendons, which remain normal!)
- •Secondary PIP joint palmar plate and collateral ligament contracture in long-standing flexion deformities
- •The Tendons Underneath Are Healthy: Unlike trigger finger, Dupuytren's is in the *skin-layer fascia* of the palm—your finger tendons underneath still bend normally, so there is no sharp snapping lock.
- •The Table-Top Check: Try laying your palm completely flat on a table; if a gap forms under your palm so it cannot touch the table, let your hand specialist know.
- •Warmth + Gentle Night Splinting: Warming the palm and doing slow, painless straightening stretches (never forceful yanking!) helps keep the cords flexible.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Individual MCP and PIP passive/active extension deficit (flexion contracture) measured in degrees via finger goniometry (Tubiana Staging I–IV).
2. Special Clinical Provocation & Neurological/Functional Tests
Hueston's Table-Top Test (positive when the patient can no longer lay the palm and fingers completely flat on a table surface; occurs at MCP contracture ≥30° or PIP contracture ≥15–20°, indicating need for needle aponeurotomy, collagenase, or fasciectomy consult!).
3. Standardized Clinical Outcome Scales & Imaging Criteria
Tubiana Classification, URAM (Unité Rhumatologique des Affections de la Main) scale, QuickDASH, and Total Active Extension deficit.
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Firm, painless (or mildly tender) palmar nodules and skin dimpling/pitting near the distal palmar crease at the base of the ring (4th) and little (5th) fingers.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Nodular / Early Cord Phase (Conservative Fascial Extensibility): Therapeutic ultrasound / paraffin warm bath, gentle transverse friction massage with vitamin E/silicone cream over palmar nodules, and sustained low-load passive finger extension stretching (tabletop press).
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in Dupuytren's Contracture.
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Tendon Differential Gliding & Intrinsic Balance Phase: Active finger abduction/extension (finger spread), Six-Pack tendon gliding, thumb opposition, and nocturnal static-progressive palmar extension splint (worn at night to maintain myofibroblast length without triggering daytime inflammation).
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints.
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Post-Intervention (Fasciectomy / Needle Aponeurotomy) Rehabilitation Phase: Immediate (Day 2–5) edema control, scar mobilization, custom night extension splinting for 3–6 months, and active flexion/extension restoration.
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •The Tendons Underneath Are Healthy: Unlike trigger finger, Dupuytren's is in the *skin-layer fascia* of the palm—your finger tendons underneath still bend normally, so there is no sharp snapping lock.
- •Calm Protection & Gentle Start: During the initial stage of Palmar Fascia Thickening, avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •The Table-Top Check: Try laying your palm completely flat on a table; if a gap forms under your palm so it cannot touch the table, let your hand specialist know.
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Warmth + Gentle Night Splinting: Warming the palm and doing slow, painless straightening stretches (never forceful yanking!) helps keep the cords flexible.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Six-Pack Differential Flexor Tendon Gliding (FDS & FDP Excursion)
1. Step-by-Step Finger Tendon Gliding (Hook, Straight & Full Fist)
Sequential progression through Straight Hand, Tabletop (intrinsic-plus), Hook Fist (maximum FDS/FDP differential glide), Full Fist, and Straight Fist positions. Prevents peritendinous adhesions within the carpal tunnel and fibro-osseous digital sheaths. Specifically indicated in Dupuytren's Contracture rehabilitation to optimize palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints biomechanics and neuromuscular control.
Start with your fingers straight, then bend at the knuckles (tabletop), curl just the fingertips (hook fist), make a gentle full fist, and open wide again—holding each position for 2–3 seconds. Perform smoothly within a comfortable, pain-free range to support your Palmar Fascia Thickening recovery.
 🔍 Enlarge
2. Dorsal/Palmar Interossei & Lumbrical Activation (Active Finger Abduction/Extension)
2. Tabletop Finger Spreading (Fan Out) & Opening
With the palm resting flat on a surface, actively spreading all digits apart (abduction) and bringing them back together, combined with controlled MCP/IP extension. Strengthens ulnar-innervated interossei and balances extrinsic flexors. Specifically indicated in Dupuytren's Contracture rehabilitation to optimize palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints biomechanics and neuromuscular control.
Rest your hand flat on a table. Spread your fingers wide apart like a fan, hold for 3 seconds, and slowly bring them back together without lifting your palm. Perform smoothly within a comfortable, pain-free range to support your Palmar Fascia Thickening recovery.
 🔍 Enlarge
3. Biarticular Forearm Flexor & Extensor Myofascial Stretch
3. Straight-Arm Gentle Wrist Flexor & Extensor Stretch
With the elbow in full extension, using the contralateral hand to apply a slow, sustained passive stretch into wrist flexion (for ECRB/extensors) and wrist extension (for common flexors). Reduces resting myotendinous tension. Specifically indicated in Dupuytren's Contracture rehabilitation to optimize palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints biomechanics and neuromuscular control.
Extend your arm forward with your elbow straight. Use your other hand to gently bend your wrist downward until you feel a mild stretch in your forearm, hold for 20–30 seconds, then repeat bending upward. Perform smoothly within a comfortable, pain-free range to support your Palmar Fascia Thickening recovery.
 🔍 Enlarge
4. Thenar Opposition & Carpometacarpal (CMC) Fine Motor Coordination
4. Thumb-to-Fingertip Touching Sequence
Sequential opposition of the thumb pad to the tips of the index, middle, ring, and little fingers forming an 'O' ring, followed by sliding down the 5th digit toward the distal palmar crease. Restores first web-space mobility and intrinsic precision pinch. Specifically indicated in Dupuytren's Contracture rehabilitation to optimize palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints biomechanics and neuromuscular control.
Gently touch the tip of your thumb to each fingertip one by one from your index finger to your little finger, forming a neat 'O' shape each time, then open your hand wide. Perform smoothly within a comfortable, pain-free range to support your Palmar Fascia Thickening recovery.
 🔍 Enlarge
5. Radiocarpal & Midcarpal Active/Eccentric Flexion and Extension
5. Table-Edge Wrist Bending Up and Down
Controlled sagittal plane wrist flexion and extension with the forearm supported on a table edge and digits relaxed. Restores radiocarpal/midcarpal roll-and-glide mechanics and stimulates aligned collagen synthesis in forearm tendons. Specifically indicated in Dupuytren's Contracture rehabilitation to optimize palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints biomechanics and neuromuscular control.
Rest your forearm on a table with your wrist hanging comfortably over the edge. Slowly lift your hand upward toward the ceiling, hold for 3 seconds, then lower it gently downward. Perform smoothly within a comfortable, pain-free range to support your Palmar Fascia Thickening recovery.
 🔍 Enlarge
6. Proximal & Distal Radioulnar Joint (PRUJ/DRUJ) Supination and Pronation
6. Elbow-at-Side Palm Up and Palm Down Rotation
Isolated forearm rotation with the elbow flexed at 90° and adducted against the trunk to eliminate compensatory glenohumeral rotation. Restores radial head spinning and distal radioulnar translation. Specifically indicated in Dupuytren's Contracture rehabilitation to optimize palmar aponeurosis (pretendinous bands, natatory ligaments, and spiral/central cords) and 4th–5th digit MCP/PIP joints biomechanics and neuromuscular control.
Keep your elbow bent at a right angle and tucked closely against your waist. Slowly turn your palm upward toward the ceiling, hold for 3 seconds, then turn your palm downward toward the floor. Perform smoothly within a comfortable, pain-free range to support your Palmar Fascia Thickening recovery.
Movements to Avoid & Strict Precautions
1. Forceful, Painful Yanking on the Contracted Finger (Micro-Tears Trigger TGF-β and Accelerate Fibrosis!)
1. Forcefully yanking or bending the curled finger backward to the point of pain (triggers faster scar thickening!)
2. Using Heavy Vibrating Tools or Tight Unpadded Gripping (Barbells, Hammers, Racket Handles)
2. Gripping unpadded tools, heavy barbells, or steering wheels without padded gloves
3. Waiting Until the Finger Touches the Palm Before Seeking Specialist Care
3. Waiting until the middle finger joint is bent past 30–45 degrees before seeing a hand specialist
4. Discontinuing the Night Extension Splint Early After Hand Procedure
4. Stopping your night straightening splint too early after a Dupuytren's procedure
Dupuytren's Contracture (Palmar Fibromatosis) — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

What Is Dupuytren's Contracture (Palmar Fibromatosis) and How Is It Treated?
Dupuytren's contracture (palmar fascial fibromatosis) is a benign, progressive fibroproliferative disorder of the palmar aponeurosis in which fibroblasts differentiate into contractile myofibroblasts (producing excess Type III collagen via TGF-β signaling). It progresses from painless palmar nodules and skin pitting near the distal palmar crease to longitudinal fibrous cords that draw the ring (4th) and little (5th) fingers into progressive MCP and PIP flexion contracture.
Dupuytren's contracture (palmar fascia thickening) is a condition where the connective tissue layer just under the skin of your palm thickens into small firm knots (nodules) and cords that gradually pull the ring and little fingers inward so they cannot straighten completely.
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

Tendon and Nerve Gliding Exercises | Carpal Tunnel and Hand Rehabilitation
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Nodular / Early Cord Phase (Conservative Fascial Extensibility): Therapeutic ultrasound / paraffin warm bath, gentle transverse friction massage with vitamin E/silicone cream over palmar nodules, and sustained low-load passive finger extension stretching (tabletop press).
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: The Tendons Underneath Are Healthy: Unlike trigger finger, Dupuytren's is in the *skin-layer fascia* of the palm—your finger tendons underneath still bend normally, so there is no sharp snapping lock.

Joint Protection and Hand Rehabilitation Exercises in Rheumatic Diseases
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Tendon Differential Gliding & Intrinsic Balance Phase: Active finger abduction/extension (finger spread), Six-Pack tendon gliding, thumb opposition, and nocturnal static-progressive palmar extension splint (worn at night to maintain myofibroblast length without triggering daytime inflammation).
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: The Table-Top Check: Try laying your palm completely flat on a table; if a gap forms under your palm so it cannot touch the table, let your hand specialist know.
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

Wrist Clinical Examination and Functional Assessment
Goniometric ROM & Postural / Kinematic Analysis: Individual MCP and PIP passive/active extension deficit (flexion contracture) measured in degrees via finger goniometry (Tubiana Staging I–IV).

Wrist Joint Goniometric Measurement (Flexion, Extension, Radial/Ulnar Deviation)
Special Clinical Provocation & Neurological/Functional Tests: Hueston's Table-Top Test (positive when the patient can no longer lay the palm and fingers completely flat on a table surface; occurs at MCP contracture ≥30° or PIP contracture ≥15–20°, indicating need for needle aponeurotomy, collagenase, or fasciectomy consult!).