SLAP Lesion (Superior Glenoid Labrum Tear)Shoulder Socket Cartilage Rim Tear (SLAP Lesion (Superior Labral Tear))
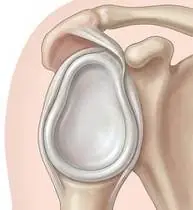
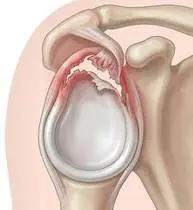
SLAP Lesion (Superior Glenoid Labrum Tear) — Overview
A SLAP Lesion (Superior Labrum Anterior to Posterior) is a detachment or tearing of the superior fibrocartilaginous glenoid labrum where the long head of the biceps brachii tendon (LHBT) anchors to the supraglenoid tubercle. Classified by Snyder (Types I–IV; Type II detachment of the biceps-labral anchor is the most clinically significant). In overhead athletes (baseball, volleyball, tennis, swimming), it is driven by the 'Peel-Back' mechanism during late cocking (90° abduction + maximal external rotation) combined with GIRD (Glenohumeral Internal Rotation Deficit from posterior capsule tightness) and SICK Scapula.
A SLAP lesion (superior shoulder labral tear) is a tear at the top rim (12 o'clock position) of the rubbery cartilage ring (labrum) that deepens your shoulder socket, right where the long head of the biceps tendon attaches.
Primary Causes & Biomechanics
Key Points You Should Know
- •Peel-Back Mechanism: In 90° abduction and maximal external rotation, the biceps tendon twists posteriorly and peels the superior labrum off the glenoid rim
- •Traction/compression mechanisms: falling onto an outstretched arm (FOOSH) or sudden heavy downward traction on the arm (catching a heavy falling weight)
- •GIRD (Glenohumeral Internal Rotation Deficit ≥20°) and posterior inferior capsule contracture shifting the humeral head posterosuperiorly
- •Why the Biceps Tendon Pulls on the Tear: Because one of your biceps tendons attaches directly to the top of that cartilage ring inside the shoulder, heavy bicep curls or reaching far behind your back pulls directly on the SLAP tear!
- •Fixing Back-of-Shoulder Tightness: When the back of the shoulder joint is tight, the ball shifts upward and grinds the top cartilage ring; gentle cross-body stretches center the ball again.
- •Shoulder Blade + Core Power: When your shoulder blade and core muscles are strong, your shoulder socket moves smoothly with your arm during overhead reach or sports.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Glenohumeral Internal Rotation vs. External Rotation at 90° abduction (assessing Total Rotational Motion and GIRD).
2. Special Clinical Provocation & Neurological/Functional Tests
O'Brien's Active Compression Test (deep shoulder pain at 90° flexion, 10–15° adduction with thumb down [internal rotation] that is relieved with palm up [external rotation]!), Biceps Load II Test (Kim's test — high specificity!), Crank Test, Speed's & Yergason's Tests (biceps tendon), and Scapular Dyskinesis screen.
3. Standardized Clinical Outcome Scales & Imaging Criteria
ASES Shoulder Score, Kerlan-Jobe Orthopaedic Clinic (KJOC) Overhead Athlete Score, and MR Arthrogram (MRA — gold standard to distinguish a true SLAP tear from a normal sublabral foramen/Buford complex).
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Deep, poorly localized pain, clicking, catching, or mechanical popping deep inside the shoulder, worst during overhead throwing/serving (late cocking phase), lifting heavy objects at arm's length, or pushing up.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Peel-Back Protection, Scapular Reset & GIRD Stretching (Weeks 1–3): Avoid 90/90 abduction-external rotation and heavy biceps loading (for 4–6 weeks post-SLAP repair, no active biceps contraction!); perform Codman's pendulums, scapular retraction/depression, and Gentle Cross-Body / Sleeper Stretch (for posterior capsule GIRD).
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in SLAP Lesion (Superior Labral Tear).
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Rotator Cuff Centering & Scaption Phase (Weeks 3–6): Supine wand-assisted elevation, towel-supported external rotation at 0°–30°, side-lying external rotation, and scapular plane Full-Can elevation.
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor.
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Phase 3 — Serratus Anterior, Core-to-Shoulder Kinetic Chain & Return to Throw (Week 6–16+): Closed-chain wall ball stabilization ('Serratus Plus'), lower limb/core kinetic chain transfer (50% of throwing force comes from legs/trunk!), and interval throwing progression.
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •Why the Biceps Tendon Pulls on the Tear: Because one of your biceps tendons attaches directly to the top of that cartilage ring inside the shoulder, heavy bicep curls or reaching far behind your back pulls directly on the SLAP tear!
- •Calm Protection & Gentle Start: During the initial stage of Shoulder Socket Cartilage Rim Tear, avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Fixing Back-of-Shoulder Tightness: When the back of the shoulder joint is tight, the ball shifts upward and grinds the top cartilage ring; gentle cross-body stretches center the ball again.
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Shoulder Blade + Core Power: When your shoulder blade and core muscles are strong, your shoulder socket moves smoothly with your arm during overhead reach or sports.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Codman's Pendulum Glenohumeral Decompression Exercise
1. Bent-Over Gentle Arm Pendulum Swings
Trunk flexed forward 45°–60° with the sound hand supported on a table while the affected arm hangs completely relaxed like a plumb line. Momentum from gentle trunk sway creates passive glenohumeral distraction and synovial lubrication without rotator cuff firing. Specifically indicated in SLAP Lesion (Superior Labral Tear) rehabilitation to optimize superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor biomechanics and neuromuscular control.
Lean forward supporting your healthy hand on a table and let your affected arm hang completely relaxed toward the floor. Gently sway your body to let the arm swing in small pain-free circles without using your shoulder muscles. Perform smoothly within a comfortable, pain-free range to support your Shoulder Socket Cartilage Rim Tear recovery.
 🔍 Enlarge
2. Scapulothoracic Retraction & Depression (Middle/Lower Trapezius & Rhomboids)
2. Shoulder Blade Squeeze (Postural Alignment)
Adduction and depression of the scapulae via the middle/lower trapezius and rhomboids while inhibiting upper trapezius overactivity. Corrects anterior scapular tilt, widens the subacromial outlet, and unloads the anterior thoracic column. Specifically indicated in SLAP Lesion (Superior Labral Tear) rehabilitation to optimize superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor biomechanics and neuromuscular control.
Sit or stand tall. Keep your shoulders relaxed away from your ears, gently draw your shoulder blades together and slightly downward toward your back pockets, hold for 5 seconds, and release. Perform smoothly within a comfortable, pain-free range to support your Shoulder Socket Cartilage Rim Tear recovery.
 🔍 Enlarge
3. Towel-Supported Glenohumeral External Rotation (Infraspinatus & Teres Minor)
3. Outward Forearm Rotation with Rolled Towel Under Elbow
External rotation performed at 90° elbow flexion with a rolled towel placed between the elbow and trunk (20°–30° scaption). Enhances infraspinatus/teres minor recruitment while preventing superior humeral head migration and deltoid shear. Specifically indicated in SLAP Lesion (Superior Labral Tear) rehabilitation to optimize superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor biomechanics and neuromuscular control.
Place a small rolled towel between your elbow and your side with your elbow bent at 90 degrees. Keeping your elbow pressed gently against the towel, rotate your forearm outward, hold for 3 seconds, and return slowly. Perform smoothly within a comfortable, pain-free range to support your Shoulder Socket Cartilage Rim Tear recovery.
 🔍 Enlarge
4. Closed-Chain Wall Ball Stabilization & Serratus Anterior Protraction
4. Wall Ball Circles & Shoulder Blade Control
Rhythmic stabilization and small circular perturbations with the hand pressing a soft ball against the wall at shoulder height. Stimulates glenohumeral joint mechanoreceptors, serratus anterior upward rotation, and rotator cuff co-contraction. Specifically indicated in SLAP Lesion (Superior Labral Tear) rehabilitation to optimize superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor biomechanics and neuromuscular control.
Hold a small soft ball against the wall at chest or shoulder height with your elbow nearly straight. Gently press into the ball and trace small, controlled clockwise and counterclockwise circles. Perform smoothly within a comfortable, pain-free range to support your Shoulder Socket Cartilage Rim Tear recovery.
 🔍 Enlarge
5. Side-Lying Glenohumeral External Rotation (Isotonic Posterior Cuff)
5. Side-Lying Outward Arm Rotation
Isotonic external rotation against gravity in side-lying with a towel roll under the axilla. Elicits maximal isolated EMG activation of the infraspinatus and teres minor with minimal supraspinatus and deltoid overload. Specifically indicated in SLAP Lesion (Superior Labral Tear) rehabilitation to optimize superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor biomechanics and neuromuscular control.
Lie on your uninjured side with a small towel under your top elbow, bent at 90 degrees. Slowly rotate your forearm upward toward the ceiling while keeping your elbow tucked at your side, pause, and lower slowly. Perform smoothly within a comfortable, pain-free range to support your Shoulder Socket Cartilage Rim Tear recovery.
 🔍 Enlarge
6. Scapular Plane 'Full-Can' Elevation (30° Scaption, Thumb Up)
6. Thumb-Up Diagonal Arm Raise (Full-Can)
Active elevation in the scapular plane (30° anterior to the frontal plane) with external rotation (thumb pointing up) to shoulder height. Clears the greater tuberosity beneath the acromion and optimizes the deltoid-rotator cuff force couple. Specifically indicated in SLAP Lesion (Superior Labral Tear) rehabilitation to optimize superior glenoid labrum (10 o'clock to 2 o'clock position) and long head of the biceps brachii tendon anchor biomechanics and neuromuscular control.
Stand tall with your thumb pointing upward like a 'thumbs-up' sign. Raise your arm slightly forward and to the side (at a 30-degree angle) up to shoulder height without shrugging your shoulder, then lower slowly. Perform smoothly within a comfortable, pain-free range to support your Shoulder Socket Cartilage Rim Tear recovery.
Movements to Avoid & Strict Precautions
1. Cocking the Arm High and Far Back (90° Abduction + Maximal External Rotation / 'Peel-Back' Position!)
1. Pulling your arm far back in a throwing cocked position or reaching twisted into the back seat of a car
2. Heavy Bicep Curls, Chin-Ups, or Catching Heavy Falling Loads (In Weeks 1–6 Post-Repair, Active Biceps Is Forbidden!)
2. Doing heavy bicep curls, pull-ups, or lifting heavy bags with a straight arm
3. Deep Bench Presses (Elbows Dropping Behind the Body Line) or Triceps Dips
3. Doing deep bench presses, chest flyes, or chair dips that let your elbows drop behind your back
4. Overhead Serving or Pitching Before Resolving Posterior Shoulder Tightness (GIRD)
4. Returning to tennis serves, volleyball spikes, or pitching while the shoulder still feels tight or clicks
SLAP Lesion (Superior Glenoid Labrum Tear) — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

What Is a SLAP Lesion (Superior Shoulder Labral Tear)? Symptoms and Mechanism
A SLAP Lesion (Superior Labrum Anterior to Posterior) is a detachment or tearing of the superior fibrocartilaginous glenoid labrum where the long head of the biceps brachii tendon (LHBT) anchors to the supraglenoid tubercle. Classified by Snyder (Types I–IV; Type II detachment of the biceps-labral anchor is the most clinically significant). In overhead athletes (baseball, volleyball, tennis, swimming), it is driven by the 'Peel-Back' mechanism during late cocking (90° abduction + maximal external rotation) combined with GIRD (Glenohumeral Internal Rotation Deficit from posterior capsule tightness) and SICK Scapula.
A SLAP lesion (superior shoulder labral tear) is a tear at the top rim (12 o'clock position) of the rubbery cartilage ring (labrum) that deepens your shoulder socket, right where the long head of the biceps tendon attaches.
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

3 Core Rehabilitation Exercises for a SLAP Lesion (Shoulder Labral Tear)
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Peel-Back Protection, Scapular Reset & GIRD Stretching (Weeks 1–3): Avoid 90/90 abduction-external rotation and heavy biceps loading (for 4–6 weeks post-SLAP repair, no active biceps contraction!); perform Codman's pendulums, scapular retraction/depression, and Gentle Cross-Body / Sleeper Stretch (for posterior capsule GIRD).
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: Why the Biceps Tendon Pulls on the Tear: Because one of your biceps tendons attaches directly to the top of that cartilage ring inside the shoulder, heavy bicep curls or reaching far behind your back pulls directly on the SLAP tear!

SLAP Lesion Diagnosis, Conservative Physiotherapy, and Post-Surgical Rehab
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Rotator Cuff Centering & Scaption Phase (Weeks 3–6): Supine wand-assisted elevation, towel-supported external rotation at 0°–30°, side-lying external rotation, and scapular plane Full-Can elevation.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Fixing Back-of-Shoulder Tightness: When the back of the shoulder joint is tight, the ball shifts upward and grinds the top cartilage ring; gentle cross-body stretches center the ball again.
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

O'Brien's Active Compression Test — SLAP Lesion Clinical Assessment
Goniometric ROM & Postural / Kinematic Analysis: Glenohumeral Internal Rotation vs. External Rotation at 90° abduction (assessing Total Rotational Motion and GIRD).

Yergason's Test — Long Head of Biceps and SLAP Complex Examination
Special Clinical Provocation & Neurological/Functional Tests: O'Brien's Active Compression Test (deep shoulder pain at 90° flexion, 10–15° adduction with thumb down [internal rotation] that is relieved with palm up [external rotation]!), Biceps Load II Test (Kim's test — high specificity!), Crank Test, Speed's & Yergason's Tests (biceps tendon), and Scapular Dyskinesis screen.
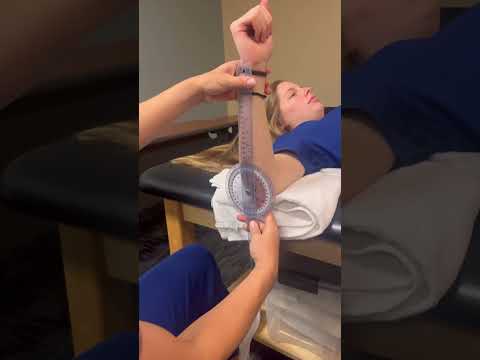
Shoulder Joint Goniometric Measurement (Flexion, Abduction, Internal & External Rotation)
Standardized Clinical Outcome Scales & Imaging Criteria: ASES Shoulder Score, Kerlan-Jobe Orthopaedic Clinic (KJOC) Overhead Athlete Score, and MR Arthrogram (MRA — gold standard to distinguish a true SLAP tear from a normal sublabral foramen/Buford complex).