ACL (Anterior Cruciate Ligament) RuptureTorn Knee Anterior Cruciate Ligament (ACL (Anterior Cruciate Ligament) Rupture)
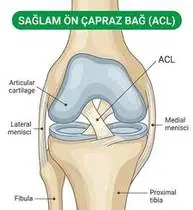
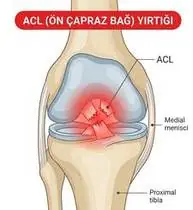
ACL (Anterior Cruciate Ligament) Rupture — Overview
Anterior Cruciate Ligament (ACL) rupture is a devastating intra-articular knee injury (~70% occurring via a non-contact mechanism: landing or cutting on a near-extended knee with dynamic knee valgus, hip internal rotation/adduction, and tibial rotation). Because the ACL provides 85% of restraint to anterior tibial translation and controls rotational pivot stability, rehabilitation (whether conservative 'coper' rehab or post-ACLR reconstruction) must respect biological Graft Ligamentization (necrosis/revascularization weakest at Weeks 6–12!) and follow strict criterion-based (not just time-based!) progression.
An ACL rupture (torn anterior cruciate ligament) is a tear of the main central stabilizing ligament inside your knee that stops your shinbone from sliding forward and keeps your knee from buckling when you pivot, cut, or land from a jump.
Primary Causes & Biomechanics
Key Points You Should Know
- •Non-contact biomechanical collapse: quadriceps-dominant landing at <20–30° knee flexion combined with dynamic valgus and trunk lateral lean
- •Open-Kinetic-Chain (OKC) shear physics: unconstrained open-chain knee extension between 45° and 0° creates peak anterior tibial shear stress via patellar tendon pull; Closed-Kinetic-Chain (CKC) squats/bridges co-activate the hamstrings (the ACL's primary agonist!)
- •Concomitant injuries ('Unhappy Triad'): medial meniscus / lateral meniscus tears and MCL sprain
- •Rule #1: Get Your Knee 100% Straight First! In the first 2 weeks after injury or surgery, propping your heel on a rolled towel (with nothing under the knee!) so the knee straightens completely is the most important step for a normal walk.
- •Hamstrings Are Your ACL's Best Friend: The muscles at the back of your thigh (hamstrings) pull the shinbone backward—doing exactly the same job as the ACL!
- •The 9-Month Biological Rule: After ACL surgery, the new ligament graft transforms inside the knee over 9 months; even if your leg feels strong at 5 months, waiting the full 9 months cuts re-tear risk in half.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Full 0° Passive Knee Extension (matching the contralateral hyperextension within Week 1–2 is the #1 predictor of avoiding arthrofibrosis/cyclops lesion!) and progressive flexion ROM.
2. Special Clinical Provocation & Neurological/Functional Tests
Lachman Test at 20–30° flexion (gold standard clinical test: 95% sensitivity!), Pivot-Shift Test (most specific for rotational instability), Anterior Drawer Test at 90°, and Lelli's Lever Sign.
3. Standardized Clinical Outcome Scales & Imaging Criteria
IKDC Subjective Knee Form, KOOS, Tegner Lysholm Score, Isokinetic Quadriceps/Hamstring LSI (>90%), and 4-Test Hop Battery.
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Sudden audible/palpable 'pop' during a cutting, pivoting, or landing movement, followed by rapid, tense knee swelling (hemarthrosis) within 1–2 hours and inability to continue play.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Pre-Hab / Early Post-Op Extension, Effusion & Quad Awakening (Weeks 1–2): Cryotherapy + elevation, heel prop for full 0° passive extension, isometric quadriceps sets, 4-way straight leg raises (with zero extensor lag!), ankle pumps, and controlled supine heel slides.
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in ACL (Anterior Cruciate Ligament) Rupture.
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Closed-Kinetic-Chain (CKC) & Hamstring/Gluteal Agonist Phase (Weeks 2–6): Protected 0°–45° wall mini-squats, supine pelvic bridging (recruiting the hamstrings to pull the tibia posteriorly and protect the ACL!), side-lying/standing hip abduction, and chair sit-to-stand.
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers.
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Phase 3–4 — Neuromuscular Proprioception, Deceleration & RTS Criteria (Week 6–36+): Single-leg/tandem balance & perturbation training, progressive strength (Quad & Hamstring LSI ≥90%), and return to pivoting sport no earlier than 9 months post-ACLR (each month waited up to 9 months reduces re-tear risk by 51%!).
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •Rule #1: Get Your Knee 100% Straight First! In the first 2 weeks after injury or surgery, propping your heel on a rolled towel (with nothing under the knee!) so the knee straightens completely is the most important step for a normal walk.
- •Calm Protection & Gentle Start: During the initial stage of Torn Knee Anterior Cruciate Ligament, avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Hamstrings Are Your ACL's Best Friend: The muscles at the back of your thigh (hamstrings) pull the shinbone backward—doing exactly the same job as the ACL!
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •The 9-Month Biological Rule: After ACL surgery, the new ligament graft transforms inside the knee over 9 months; even if your leg feels strong at 5 months, waiting the full 9 months cuts re-tear risk in half.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Isometric Quadriceps Setting (Popliteal Towel Press)
1. Under-Knee Towel Press (Quadriceps Tightening)
Isometric compression of a rolled towel beneath the popliteal fossa into the surface with simultaneous ankle dorsiflexion. Activates the Vastus Medialis Obliquus (VMO) and overcomes arthrogenic muscle inhibition with 0° joint shear stress. Specifically indicated in ACL (Anterior Cruciate Ligament) Rupture rehabilitation to optimize anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers biomechanics and neuromuscular control.
Place a small rolled towel under your knee while lying on your back or sitting with your leg straight. Pull your toes toward you while firmly pressing the back of your knee down into the towel, hold for 5 seconds, and relax while exhaling. Perform smoothly within a comfortable, pain-free range to support your Torn Knee Anterior Cruciate Ligament recovery.
 🔍 Enlarge
2. Straight Leg Raise (SLR — Multi-Plane Isometric Knee Lock)
2. Supine Straight Leg Raise
Maintaining the knee locked in full extension (0°) with ankle dorsiflexion while elevating the lower extremity to 45° hip flexion. Strengthens the quadriceps and iliopsoas complex without compressing or shearing the articular surfaces. Specifically indicated in ACL (Anterior Cruciate Ligament) Rupture rehabilitation to optimize anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers biomechanics and neuromuscular control.
Bend your healthy knee with the foot flat on the bed. Tighten the thigh muscle of your affected leg to lock the knee straight, lift the leg to the height of the opposite knee, hold for 3 seconds, and lower slowly. Perform smoothly within a comfortable, pain-free range to support your Torn Knee Anterior Cruciate Ligament recovery.
 🔍 Enlarge
3. Protected Closed-Kinetic-Chain Wall Mini-Squat (0°–40° Safe Arc)
3. Wall-Supported Safe Mini-Squat
Closed-kinetic-chain bilateral knee flexion in the safe 0°–40° arc with the back supported against a wall. Promotes quadriceps-hamstring-gluteal co-contraction and joint proprioception without excessive patellofemoral compression. Specifically indicated in ACL (Anterior Cruciate Ligament) Rupture rehabilitation to optimize anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers biomechanics and neuromuscular control.
Lean your back flat against a wall with your feet shoulder-width apart. Slowly bend your knees slightly (30–40 degrees, keeping knees behind toes), hold for 5 seconds, and push back up. Perform smoothly within a comfortable, pain-free range to support your Torn Knee Anterior Cruciate Ligament recovery.
 🔍 Enlarge
4. Side-Lying Hip Abduction (Gluteus Medius & Frontal Plane Control)
4. Side-Lying Leg Lift (Outer Hip Strengthening)
Isolated strengthening of the gluteus medius in slight hip extension and neutral rotation. Prevents contralateral pelvic drop (Trendelenburg) and reduces dynamic knee valgus and medial compartment adduction moments. Specifically indicated in ACL (Anterior Cruciate Ligament) Rupture rehabilitation to optimize anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers biomechanics and neuromuscular control.
Lie on your side with your bottom leg slightly bent for balance. Keep your top leg straight and slightly back, lift it up toward the ceiling without rolling your pelvis backward, hold for 3 seconds, and lower slowly. Perform smoothly within a comfortable, pain-free range to support your Torn Knee Anterior Cruciate Ligament recovery.
 🔍 Enlarge
5. Supine Active-Assisted Heel Slide & Synovial Diffusion Mobilization
5. Supine Heel Slide (Gentle Knee & Hip Bending)
Controlled flexion and extension of the lower extremity by sliding the heel along the support surface without axial weight-bearing. Stimulates synovial fluid diffusion across avascular cartilage and prevents capsular adhesions. Specifically indicated in ACL (Anterior Cruciate Ligament) Rupture rehabilitation to optimize anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers biomechanics and neuromuscular control.
While lying on your back, slowly slide your heel along the bed sheet toward your hip within a comfortable, pain-free angle, hold for 3 seconds, and gently slide it back out straight. Perform smoothly within a comfortable, pain-free range to support your Torn Knee Anterior Cruciate Ligament recovery.
 🔍 Enlarge
6. Supine Lumbopelvic Bridging (Gluteus Maximus & Posterior Chain Co-Contraction)
6. Supine Hip Bridge (Controlled Pelvic Lift)
From hook-lying with transversus abdominis pre-activation, elevating the pelvis until hips, pelvis, and shoulders form a neutral diagonal line. Strengthens the gluteus maximus, hamstrings, and erector spinae synergy without lumbar hyperlordosis. Specifically indicated in ACL (Anterior Cruciate Ligament) Rupture rehabilitation to optimize anterior cruciate ligament (anteromedial and posterolateral bundles), tibiofemoral joint, and dynamic neuromuscular knee stabilizers biomechanics and neuromuscular control.
Lie on your back with your knees bent and feet flat hip-width apart. Gently tighten your tummy and glutes, lift your hips until your body forms a straight line from shoulders to knees, hold for 5 seconds, and lower slowly. Perform smoothly within a comfortable, pain-free range to support your Torn Knee Anterior Cruciate Ligament recovery.
Movements to Avoid & Strict Precautions
1. Propping a Pillow Under the Bent Knee in Early Weeks (Causes Permanent Extension Loss!)
1. Putting a pillow under the back of your knee (always put the pillow under your HEEL so the knee hangs straight!)
2. Unconstrained Open-Chain Leg Extension Machine With Ankle Weights at 30°–0° in Weeks 1–6
2. Doing seated leg extensions with weights near full straightening in the first 6 weeks (pulls on the healing graft!)
3. Pivoting, Cutting, or Twisting on the Planted Foot During Early/Mid Rehab
3. Twisting or pivoting on your operated leg before passing return-to-sport tests
4. Returning to Competitive Pivoting Sports (Soccer, Basketball, Skiing) Before 9 Months Post-Op
4. Returning to soccer, basketball, or skiing before 9 months and 90% strength symmetry
ACL (Anterior Cruciate Ligament) Rupture — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

What Is an Anterior Cruciate Ligament (ACL) Rupture? Mechanism and Symptoms
Anterior Cruciate Ligament (ACL) rupture is a devastating intra-articular knee injury (~70% occurring via a non-contact mechanism: landing or cutting on a near-extended knee with dynamic knee valgus, hip internal rotation/adduction, and tibial rotation). Because the ACL provides 85% of restraint to anterior tibial translation and controls rotational pivot stability, rehabilitation (whether conservative 'coper' rehab or post-ACLR reconstruction) must respect biological Graft Ligamentization (necrosis/revascularization weakest at Weeks 6–12!) and follow strict criterion-based (not just time-based!) progression.
An ACL rupture (torn anterior cruciate ligament) is a tear of the main central stabilizing ligament inside your knee that stops your shinbone from sliding forward and keeps your knee from buckling when you pivot, cut, or land from a jump.
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

ACL Rehabilitation Strengthening and Proprioception Exercises
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Pre-Hab / Early Post-Op Extension, Effusion & Quad Awakening (Weeks 1–2): Cryotherapy + elevation, heel prop for full 0° passive extension, isometric quadriceps sets, 4-way straight leg raises (with zero extensor lag!), ankle pumps, and controlled supine heel slides.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: Rule #1: Get Your Knee 100% Straight First! In the first 2 weeks after injury or surgery, propping your heel on a rolled towel (with nothing under the knee!) so the knee straightens completely is the most important step for a normal walk.

Early-Phase Physiotherapy Exercises After ACL Reconstruction Surgery
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Closed-Kinetic-Chain (CKC) & Hamstring/Gluteal Agonist Phase (Weeks 2–6): Protected 0°–45° wall mini-squats, supine pelvic bridging (recruiting the hamstrings to pull the tibia posteriorly and protect the ACL!), side-lying/standing hip abduction, and chair sit-to-stand.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Hamstrings Are Your ACL's Best Friend: The muscles at the back of your thigh (hamstrings) pull the shinbone backward—doing exactly the same job as the ACL!
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

Anterior Drawer Test — Anterior Cruciate Ligament (ACL) Clinical Examination
Goniometric ROM & Postural / Kinematic Analysis: Full 0° Passive Knee Extension (matching the contralateral hyperextension within Week 1–2 is the #1 predictor of avoiding arthrofibrosis/cyclops lesion!) and progressive flexion ROM.

Lachman Test — ACL Laxity and End-Feel Clinical Examination
Special Clinical Provocation & Neurological/Functional Tests: Lachman Test at 20–30° flexion (gold standard clinical test: 95% sensitivity!), Pivot-Shift Test (most specific for rotational instability), Anterior Drawer Test at 90°, and Lelli's Lever Sign.

Lelli (Lever Sign) Test — ACL Rupture Clinical Assessment
Standardized Clinical Outcome Scales & Imaging Criteria: IKDC Subjective Knee Form, KOOS, Tegner Lysholm Score, Isokinetic Quadriceps/Hamstring LSI (>90%), and 4-Test Hop Battery.