Congenital ScoliosisCongenital Spinal Curvature (Congenital Scoliosis)
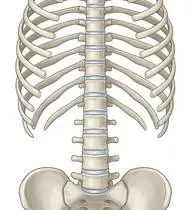
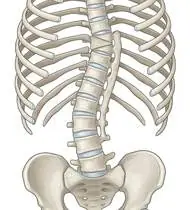
Congenital Scoliosis — Overview
Congenital Scoliosis is a structural lateral spinal curvature present at birth resulting from anomalous embryonic vertebral development during weeks 4 to 6 of gestation (when the heart, kidneys, and spinal cord also form!). It is classified by Winter and McMaster into 3 embryological defects: 1) Failure of Formation (Hemivertebra: wedge-shaped half-vertebra acting as an asymmetric growth wedge), 2) Failure of Segmentation (Unsegmented Bar: a solid bony tether on the concave side that cannot grow while the convex side grows!), and 3) Mixed Defects (Unilateral Unsegmented Bar WITH a Contralateral Hemivertebra — THE WORST PROGNOSIS, progressing >5–10° per year from infancy!). Crucially, 60% of children with congenital scoliosis have associated VACTERL / Renal (20–30%), Cardiac (10–15%), or Intraspinal (Tethered Cord / Diastematomyelia in 20–40%) anomalies requiring mandatory whole-spine MRI, renal ultrasound, and echocardiogram!
Congenital scoliosis (congenital spinal curvature) is a spinal curve caused by one or more spinal bones forming as a triangular half-bone (hemivertebra) or fusing along one side (bony bar) during the first 6 weeks of pregnancy. While a pediatric spine specialist closely tracks the bony growth, specialized respiratory chest-expansion exercises, core strengthening, and playful posture training keep your child's lungs, ribcage, and flexible spine segments healthy and strong!
Primary Causes & Biomechanics
Key Points You Should Know
- •Embryonic somite defect during gestational weeks 4–6 (Failure of Formation, Failure of Segmentation, or Mixed)
- •Why Passive Bracing Alone Cannot Straighten a Bony Hemivertebra: Unlike flexible idiopathic scoliosis, a congenital osseous bar/hemivertebra is a rigid bony anomaly; bracing is used only to control flexible compensatory curves above/below or post-hemivertebra excision!
- •Thoracic Insufficiency Syndrome (TIS) Danger in Early-Onset Thoracic Curves: Because alveolar lung multiplication occurs primarily from birth to age 5–8 years, severe congenital thoracic scoliosis + fused ribs (Jarcho-Levin / spondylocostal dysostosis) restricts lung growth!
- •Why Kidney, Heart & Spine MRI Checks Are Routine (And Reassuring): Because the spine bones, kidneys, and heart all form during the exact same week in pregnancy, doctors automatically do a painless ultrasound of the kidneys and heart plus a spine MRI for every child with congenital scoliosis.
- •Protecting Lung Growth Through Chest-Opening Play: Between birth and age 8, your child's lungs are growing millions of tiny air sacs. Singing, blowing bubbles/pinwheels, swimming, and reaching overhead while breathing deeply keeps the ribcage wide and flexible!
- •Supporting the Flexible Spine Above and Below: Even when one vertebra is wedge-shaped, keeping the core muscles and the rest of the spine flexible maintains balanced head and shoulder posture.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Cobb angle measurement on serial standing/supine AP/lateral radiographs, Rib-Vertebral Angle Difference (RVAD), and trunk balance.
2. Special Clinical Provocation & Neurological/Functional Tests
Mandatory Systemic Screening Triad: 1) Whole-Spine MRI (ruling out diastematomyelia, syringomyelia, tethered cord), 2) Renal Ultrasound (ruling out unilateral renal agenesis/horseshoe kidney), and 3) Echocardiogram; plus neurological exam and chest expansion.
3. Standardized Clinical Outcome Scales & Imaging Criteria
Cobb Angle (degrees), Thoracic Spine Height (T1–T12 cm, target ≥18–22 cm for normal lung volume), and FVC.
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Spinal curvature, uneven shoulder height, tilted head/neck (if a cervical/cervicothoracic hemivertebra is present), or an asymmetric waistline/rib prominence noticed in infancy or early childhood.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Thoracic Cage Expansion & Respiratory Compliance Phase: Deep diaphragmatic and rotational costal expansion breathing (using bubble/pinwheel games and manual rib cage mobilization) to maximize alveolar lung development on the concave side!
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in Congenital Scoliosis.
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Trunk Elongation, Postural Symmetry & Compensatory Curve Control Phase: Playful axial trunk elongation (wall-supported tall standing, overhead two-handed reaching), quadruped Bird-Dog / crawling, and pelvic-shoulder girdle leveling.
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage.
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Phase 3 — Peri-Surgical (Hemivertebra Resection / Growing Rod) & Core Endurance Phase: Pre- and post-operative respiratory physiotherapy, supine pelvic bridging, scapular retraction, and safe aquatic therapy.
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •Why Kidney, Heart & Spine MRI Checks Are Routine (And Reassuring): Because the spine bones, kidneys, and heart all form during the exact same week in pregnancy, doctors automatically do a painless ultrasound of the kidneys and heart plus a spine MRI for every child with congenital scoliosis.
- •Calm Protection & Gentle Start: During the initial stage of Congenital Spinal Curvature, avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Protecting Lung Growth Through Chest-Opening Play: Between birth and age 8, your child's lungs are growing millions of tiny air sacs. Singing, blowing bubbles/pinwheels, swimming, and reaching overhead while breathing deeply keeps the ribcage wide and flexible!
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Supporting the Flexible Spine Above and Below: Even when one vertebra is wedge-shaped, keeping the core muscles and the rest of the spine flexible maintains balanced head and shoulder posture.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Thoracic Expansion Exercise (TEE) with Bilateral Arm Elevation & 3s Inspiratory Hold
1. Chest-Opening Deep Breath with Arm Raise
Synchronizing deep nasal inspiration with bilateral shoulder flexion/abduction and a 3-second end-inspiratory hold before passive/pursed-lip expiration. Opens collateral ventilation channels to prevent basal atelectasis and maintains costovertebral compliance. Specifically indicated in Congenital Scoliosis rehabilitation to optimize embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage biomechanics and neuromuscular control.
While sitting upright, breathe in deeply through your nose while opening your arms upward and outward to expand your ribcage. Hold the breath inside for 3 seconds, then exhale slowly while lowering your arms. Perform smoothly within a comfortable, pain-free range to support your Congenital Spinal Curvature recovery.
 🔍 Enlarge
2. Wall-Referenced Axial Spinal Extension & Postural Decompression
2. Wall-Supported Tall Standing & Back Alignment
Standing with heels, gluteals, thoracic spine, and occiput aligned against a wall while performing axial elongation and gentle scapular/occipital pressure. Corrects thoracic hyperkyphosis and unloads anterior vertebral bodies. Specifically indicated in Congenital Scoliosis rehabilitation to optimize embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage biomechanics and neuromuscular control.
Stand with your heels, hips, upper back, and the back of your head lightly touching a wall. Lengthen the crown of your head toward the ceiling, gently press your shoulder blades back, and hold for 5–10 seconds while breathing calmly. Perform smoothly within a comfortable, pain-free range to support your Congenital Spinal Curvature recovery.
 🔍 Enlarge
3. Quadruped Contralateral Arm-Leg Reach ('Bird-Dog' Multifidus & Deep Core)
3. All-Fours Opposite Arm & Leg Reach (Bird-Dog)
In quadruped with a neutral lumbopelvic spine and abdominal drawing-in (transversus abdominis), extending opposite upper and lower extremities horizontally without pelvic rotation or lumbar hyperextension. Minimizes spinal compressive load while maximizing multifidus recruitment. Specifically indicated in Congenital Scoliosis rehabilitation to optimize embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage biomechanics and neuromuscular control.
On your hands and knees, keep your back flat like a tabletop and gently tighten your tummy. Slowly reach one arm forward and the opposite leg straight back withoutarching your lower back, hold for 5 seconds, and switch sides. Perform smoothly within a comfortable, pain-free range to support your Congenital Spinal Curvature recovery.
 🔍 Enlarge
4. Supine Wand-Assisted (Cane) Active-Assisted Shoulder Elevation
4. Lying Cane/Stick-Assisted Two-Handed Arm Raise
In supine (scapula stabilized against the plinth and gravity eliminated in the final arc), the unaffected upper extremity guides a wand/stick to elevate the affected shoulder smoothly without deltoid-induced superior humeral shear. Specifically indicated in Congenital Scoliosis rehabilitation to optimize embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage biomechanics and neuromuscular control.
Lie on your back holding a light stick or cane with both hands. Use your healthy arm to gently guide both arms up overhead as far as comfortable, hold for 3 seconds, and slowly lower. Perform smoothly within a comfortable, pain-free range to support your Congenital Spinal Curvature recovery.
 🔍 Enlarge
5. Scapulothoracic Retraction & Depression (Middle/Lower Trapezius & Rhomboids)
5. Shoulder Blade Squeeze (Postural Alignment)
Adduction and depression of the scapulae via the middle/lower trapezius and rhomboids while inhibiting upper trapezius overactivity. Corrects anterior scapular tilt, widens the subacromial outlet, and unloads the anterior thoracic column. Specifically indicated in Congenital Scoliosis rehabilitation to optimize embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage biomechanics and neuromuscular control.
Sit or stand tall. Keep your shoulders relaxed away from your ears, gently draw your shoulder blades together and slightly downward toward your back pockets, hold for 5 seconds, and release. Perform smoothly within a comfortable, pain-free range to support your Congenital Spinal Curvature recovery.
 🔍 Enlarge
6. Diaphragmatic & Pursed-Lip Breathing (PLB — Autonomic & Ventilatory Control)
6. Calm Belly Breathing with Pursed-Lip Exhale
Slow nasal inhalation expanding the lower ribcage and abdomen (while relaxing accessory neck/shoulder muscles), followed by prolonged expiration through pursed lips at a 1:2 ratio. Prevents dynamic airway collapse, improves basal ventilation, and reduces sympathetic tone. Specifically indicated in Congenital Scoliosis rehabilitation to optimize embryonic vertebral column (Days 28–42 somite formation/segmentation: hemivertebra or unsegmented bony bar) and developing thoracic cage biomechanics and neuromuscular control.
Sit comfortably and place one hand on your chest and the other on your belly. Breathe in slowly through your nose for 2–3 seconds so your belly gently rises, then breathe out slowly for 4–6 seconds through pursed lips as if flickering a candle. Perform smoothly within a comfortable, pain-free range to support your Congenital Spinal Curvature recovery.
Movements to Avoid & Strict Precautions
1. Taking a 'Wait-and-See for 2 Years' Approach Without Serial 6-Month Spine Specialist X-Rays in Infancy
1. Skipping 6-month pediatric spine check-ups during the rapid growth of the first 3 years of life
2. Expecting a Hard Corset to Flatten a Rigid Bony Bar (A Tight Corset Can Crush the Soft Infant Ribcage!)
2. Applying an overly tight thoracic corset over fused ribs without specialist guidance
3. Contact/Collision Sports, Trampolines, or Gymnastics Somersaults (Especially in Cervical/Thoracic Anomalies)
3. Jumping on trampolines, doing somersaults, or playing tackle sports
4. Carrying Heavy One-Strapped Bags or Slouching Into the Concave Side
4. Carrying heavy backpacks or leaning into the curve
Congenital Scoliosis — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

What Is Scoliosis? Physical Therapy Process and Adams Forward Bend Test
Congenital Scoliosis is a structural lateral spinal curvature present at birth resulting from anomalous embryonic vertebral development during weeks 4 to 6 of gestation (when the heart, kidneys, and spinal cord also form!). It is classified by Winter and McMaster into 3 embryological defects: 1) Failure of Formation (Hemivertebra: wedge-shaped half-vertebra acting as an asymmetric growth wedge), 2) Failure of Segmentation (Unsegmented Bar: a solid bony tether on the concave side that cannot grow while the convex side grows!), and 3) Mixed Defects (Unilateral Unsegmented Bar WITH a Contralateral Hemivertebra — THE WORST PROGNOSIS, progressing >5–10° per year from infancy!). Crucially, 60% of children with congenital scoliosis have associated VACTERL / Renal (20–30%), Cardiac (10–15%), or Intraspinal (Tethered Cord / Diastematomyelia in 20–40%) anomalies requiring mandatory whole-spine MRI, renal ultrasound, and echocardiogram!
Congenital scoliosis (congenital spinal curvature) is a spinal curve caused by one or more spinal bones forming as a triangular half-bone (hemivertebra) or fusing along one side (bony bar) during the first 6 weeks of pregnancy. While a pediatric spine specialist closely tracks the bony growth, specialized respiratory chest-expansion exercises, core strengthening, and playful posture training keep your child's lungs, ribcage, and flexible spine segments healthy and strong!
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

3D Schroth Exercises and Brace Rehabilitation in Scoliosis
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Thoracic Cage Expansion & Respiratory Compliance Phase: Deep diaphragmatic and rotational costal expansion breathing (using bubble/pinwheel games and manual rib cage mobilization) to maximize alveolar lung development on the concave side!
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: Why Kidney, Heart & Spine MRI Checks Are Routine (And Reassuring): Because the spine bones, kidneys, and heart all form during the exact same week in pregnancy, doctors automatically do a painless ultrasound of the kidneys and heart plus a spine MRI for every child with congenital scoliosis.

Trunk Control, Balance, and Functional Home Exercises in Pediatric Rehabilitation
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Trunk Elongation, Postural Symmetry & Compensatory Curve Control Phase: Playful axial trunk elongation (wall-supported tall standing, overhead two-handed reaching), quadruped Bird-Dog / crawling, and pelvic-shoulder girdle leveling.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Protecting Lung Growth Through Chest-Opening Play: Between birth and age 8, your child's lungs are growing millions of tiny air sacs. Singing, blowing bubbles/pinwheels, swimming, and reaching overhead while breathing deeply keeps the ribcage wide and flexible!
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

What Is Scoliosis? Physical Therapy Process and Adams Forward Bend Test
Goniometric ROM & Postural / Kinematic Analysis: Cobb angle measurement on serial standing/supine AP/lateral radiographs, Rib-Vertebral Angle Difference (RVAD), and trunk balance.

Vertebral Column (Cervical & Thoracolumbar Spine) Goniometric and Tape Measurement
Special Clinical Provocation & Neurological/Functional Tests: Mandatory Systemic Screening Triad: 1) Whole-Spine MRI (ruling out diastematomyelia, syringomyelia, tethered cord), 2) Renal Ultrasound (ruling out unilateral renal agenesis/horseshoe kidney), and 3) Echocardiogram; plus neurological exam and chest expansion.