Becker Muscular Dystrophy (Pediatric BMD)Mild-Course Childhood Muscle Wasting (Becker Muscular Dystrophy (BMD))
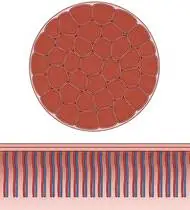
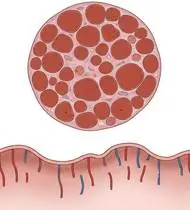
Becker Muscular Dystrophy (Pediatric BMD) — Overview
Pediatric Becker Muscular Dystrophy (BMD) presents in childhood or adolescence (typically ages 5–15) with exertional calf/thigh cramps (myalgia), mild toe-walking, calf pseudohypertrophy, or incidental elevation of serum CK—while preserving independent walking throughout childhood and young adulthood. Pediatric physiotherapy focuses on preserving full ankle dorsiflexion (preventing Achilles contracture), guiding safe non-eccentric school sports/swimming/cycling, and ensuring pediatric cardiology surveillance.
Pediatric Becker Muscular Dystrophy (childhood mild-course BMD) is a milder muscle condition in which the body makes a partially working dystrophin protein. Children with Becker MD remain active and walk independently throughout childhood and beyond! Often the main early signs are calf cramps after running and tight heel cords (tiptoe tendency)—which respond wonderfully to daily calf stretching, swimming, cycling, and smart school PE adjustments.
Primary Causes & Biomechanics
Key Points You Should Know
- •In-frame DMD gene mutation producing partially functional dystrophin protein, protecting the child from early loss of ambulation
- •First pediatric symptom is frequently exercise-induced calf cramping or myoglobinuria after PE class or soccer, plus mild Achilles tendon tightness
- •Need for early healthy postural, respiratory, and submaximal aerobic habits without social exclusion from safe peer activities
- •Smart School Gym (PE) Participation: Your child should stay active and included with friends—swimming, cycling, badminton/table tennis, and ball skills are fantastic! Just give the PE teacher a note to skip exhausting timed sprints, jump-squats, downhill running, and heavy lifting.
- •Beating Leg Cramps With Hydration & Evening Stretches: Drinking plenty of water before activity and doing a 30-second towel calf stretch every evening prevents painful night and exercise cramps.
- •Routine Heart Check-Ups: Even when a child with Becker MD runs and plays well, schedule routine pediatric cardiology check-ups as recommended by your doctor.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
North Star Ambulatory Assessment (NSAA), 6-Minute Walk Test, Timed Floor Rise, and ankle dorsiflexion goniometry (with knee extended and flexed).
2. Special Clinical Provocation & Neurological/Functional Tests
Gowers' sign screen, single-leg heel raise vs. heel walk, and annual Pediatric Echocardiogram / ECG (starting at diagnosis / age 10).
3. Standardized Clinical Outcome Scales & Imaging Criteria
NSAA, 6MWT, Ankle Dorsiflexion ROM (degrees), and Echocardiogram.
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin) moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Exercise-Induced Calf or Thigh Cramps: Aching or cramping in the calves after running or sports class in a school-aged child, often with firm, athletic-looking calves.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Achilles Flexibility & Cramp Prevention Phase: Daily long-sitting towel gastro-soleus stretches (3x30s after school/shower), ankle pumps, and hydration before/during physical activity (preventing exertional cramps!).
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin) without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in Becker Muscular Dystrophy (BMD).
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Safe Submaximal Aerobic & Core Phase: Swimming, level-ground cycling, and brisk walking (at conversational pace, Borg RPE 11–13), unloaded supine heel slides, pelvic bridging, and side-lying hip abduction.
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin).
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Phase 3 — Postural Alignment & School PE Modification Phase: Chair sit-to-stand, scapular retraction, diaphragmatic breathing, and customizing school Physical Education (participating in swimming, table tennis, cycling, and skill drills while skipping timed exhausting sprints, rope climbing, or heavy squats!).
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •Smart School Gym (PE) Participation: Your child should stay active and included with friends—swimming, cycling, badminton/table tennis, and ball skills are fantastic! Just give the PE teacher a note to skip exhausting timed sprints, jump-squats, downhill running, and heavy lifting.
- •Calm Protection & Gentle Start: During the initial stage of Mild-Course Childhood Muscle Wasting, avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Beating Leg Cramps With Hydration & Evening Stretches: Drinking plenty of water before activity and doing a 30-second towel calf stretch every evening prevents painful night and exercise cramps.
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Routine Heart Check-Ups: Even when a child with Becker MD runs and plays well, schedule routine pediatric cardiology check-ups as recommended by your doctor.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Long-Sitting Towel-Assisted Gastrocnemius-Soleus & Plantar Fascia Stretch
1. Seated Towel Calf & Foot Arch Stretch
Long-sitting with a towel looped around the metatarsal heads, applying a slow, sustained passive pull into ankle dorsiflexion. Restores gastrocnemius-soleus-Achilles length and reduces plantar fascial and equine tension. Specifically indicated in Becker Muscular Dystrophy (BMD) rehabilitation to optimize pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin) biomechanics and neuromuscular control.
Sit with your leg extended and loop a towel around the ball of your foot. Gently pull both ends of the towel toward you until you feel a comfortable stretch in your calf and sole, holding for 20–30 seconds. Perform smoothly within a comfortable, pain-free range to support your Mild-Course Childhood Muscle Wasting recovery.
 🔍 Enlarge
2. Rhythmic Active Ankle Dorsiflexion & Plantarflexion Pumping (Venous/Edema Pump)
2. Ankle Toe-Pulls and Pointing (Circulation & Swelling Pump)
Rhythmic alternating contraction of the tibialis anterior and gastrocnemius-soleus complex. Activates the deep venous calf pump to prevent deep vein thrombosis (DVT), clears distal edema, and maintains talocrural mobility. Specifically indicated in Becker Muscular Dystrophy (BMD) rehabilitation to optimize pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin) biomechanics and neuromuscular control.
While lying down or sitting with your legs supported, pull your toes and feet firmly upward toward your shins, hold for 3 seconds, then point them downward like pressing a gas pedal. Perform smoothly within a comfortable, pain-free range to support your Mild-Course Childhood Muscle Wasting recovery.
 🔍 Enlarge
3. Side-Lying Hip Abduction (Gluteus Medius & Frontal Plane Control)
3. Side-Lying Leg Lift (Outer Hip Strengthening)
Isolated strengthening of the gluteus medius in slight hip extension and neutral rotation. Prevents contralateral pelvic drop (Trendelenburg) and reduces dynamic knee valgus and medial compartment adduction moments. Specifically indicated in Becker Muscular Dystrophy (BMD) rehabilitation to optimize pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin) biomechanics and neuromuscular control.
Lie on your side with your bottom leg slightly bent for balance. Keep your top leg straight and slightly back, lift it up toward the ceiling without rolling your pelvis backward, hold for 3 seconds, and lower slowly. Perform smoothly within a comfortable, pain-free range to support your Mild-Course Childhood Muscle Wasting recovery.
 🔍 Enlarge
4. Scapulothoracic Retraction & Depression (Middle/Lower Trapezius & Rhomboids)
4. Shoulder Blade Squeeze (Postural Alignment)
Adduction and depression of the scapulae via the middle/lower trapezius and rhomboids while inhibiting upper trapezius overactivity. Corrects anterior scapular tilt, widens the subacromial outlet, and unloads the anterior thoracic column. Specifically indicated in Becker Muscular Dystrophy (BMD) rehabilitation to optimize pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin) biomechanics and neuromuscular control.
Sit or stand tall. Keep your shoulders relaxed away from your ears, gently draw your shoulder blades together and slightly downward toward your back pockets, hold for 5 seconds, and release. Perform smoothly within a comfortable, pain-free range to support your Mild-Course Childhood Muscle Wasting recovery.
 🔍 Enlarge
5. Supine Active-Assisted Heel Slide & Synovial Diffusion Mobilization
5. Supine Heel Slide (Gentle Knee & Hip Bending)
Controlled flexion and extension of the lower extremity by sliding the heel along the support surface without axial weight-bearing. Stimulates synovial fluid diffusion across avascular cartilage and prevents capsular adhesions. Specifically indicated in Becker Muscular Dystrophy (BMD) rehabilitation to optimize pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin) biomechanics and neuromuscular control.
While lying on your back, slowly slide your heel along the bed sheet toward your hip within a comfortable, pain-free angle, hold for 3 seconds, and gently slide it back out straight. Perform smoothly within a comfortable, pain-free range to support your Mild-Course Childhood Muscle Wasting recovery.
 🔍 Enlarge
6. Diaphragmatic & Pursed-Lip Breathing (PLB — Autonomic & Ventilatory Control)
6. Calm Belly Breathing with Pursed-Lip Exhale
Slow nasal inhalation expanding the lower ribcage and abdomen (while relaxing accessory neck/shoulder muscles), followed by prolonged expiration through pursed lips at a 1:2 ratio. Prevents dynamic airway collapse, improves basal ventilation, and reduces sympathetic tone. Specifically indicated in Becker Muscular Dystrophy (BMD) rehabilitation to optimize pediatric striated and cardiac muscle sarcolemma (childhood/adolescent in-frame DMD gene mutation with partial dystrophin) biomechanics and neuromuscular control.
Sit comfortably and place one hand on your chest and the other on your belly. Breathe in slowly through your nose for 2–3 seconds so your belly gently rises, then breathe out slowly for 4–6 seconds through pursed lips as if flickering a candle. Perform smoothly within a comfortable, pain-free range to support your Mild-Course Childhood Muscle Wasting recovery.
Movements to Avoid & Strict Precautions
1. Exhausting Timed Fitness Tests in School PE (Shuttle Runs, Burpees, Squat Jumps, Rope Climbing)
1. Doing exhausting school fitness tests like shuttle runs, burpees, or squat jumps to failure
2. Heavy Weightlifting or Competitive Contact/Plyometric Sports
2. Heavy barbell squats, plyometric box jumps, or downhill sprinting
3. Exercising in Hot Weather Without Drinking Water (Triggers Severe Muscle Cramps & Rhabdomyolysis!)
3. Playing sports in the heat while dehydrated
4. Walking on Tiptoes Without Daily Calf Stretching
4. Ignoring tight heel cords until the heels can no longer touch the floor
Becker Muscular Dystrophy (Pediatric BMD) — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

What Are Duchenne and Becker Muscular Dystrophy (DMD / BMD)?
Pediatric Becker Muscular Dystrophy (BMD) presents in childhood or adolescence (typically ages 5–15) with exertional calf/thigh cramps (myalgia), mild toe-walking, calf pseudohypertrophy, or incidental elevation of serum CK—while preserving independent walking throughout childhood and young adulthood. Pediatric physiotherapy focuses on preserving full ankle dorsiflexion (preventing Achilles contracture), guiding safe non-eccentric school sports/swimming/cycling, and ensuring pediatric cardiology surveillance.
Pediatric Becker Muscular Dystrophy (childhood mild-course BMD) is a milder muscle condition in which the body makes a partially working dystrophin protein. Children with Becker MD remain active and walk independently throughout childhood and beyond! Often the main early signs are calf cramps after running and tight heel cords (tiptoe tendency)—which respond wonderfully to daily calf stretching, swimming, cycling, and smart school PE adjustments.
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

Physiotherapy, Submaximal Exercise, and Contracture Management in Muscular Dystrophies
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Achilles Flexibility & Cramp Prevention Phase: Daily long-sitting towel gastro-soleus stretches (3x30s after school/shower), ankle pumps, and hydration before/during physical activity (preventing exertional cramps!).
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: Smart School Gym (PE) Participation: Your child should stay active and included with friends—swimming, cycling, badminton/table tennis, and ball skills are fantastic! Just give the PE teacher a note to skip exhausting timed sprints, jump-squats, downhill running, and heavy lifting.

Home Exercises in Pediatric Neurological Conditions (CP, Spina Bifida, Brachial Plexus)
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Safe Submaximal Aerobic & Core Phase: Swimming, level-ground cycling, and brisk walking (at conversational pace, Borg RPE 11–13), unloaded supine heel slides, pelvic bridging, and side-lying hip abduction.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Beating Leg Cramps With Hydration & Evening Stretches: Drinking plenty of water before activity and doing a 30-second towel calf stretch every evening prevents painful night and exercise cramps.
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

Gowers' Sign (Gowers' Maneuver) — Clinical Examination of Proximal Pelvic Weakness
Goniometric ROM & Postural / Kinematic Analysis: North Star Ambulatory Assessment (NSAA), 6-Minute Walk Test, Timed Floor Rise, and ankle dorsiflexion goniometry (with knee extended and flexed).

Classic Gowers' Rising Test Assessment in Duchenne and Becker Muscular Dystrophy
Special Clinical Provocation & Neurological/Functional Tests: Gowers' sign screen, single-leg heel raise vs. heel walk, and annual Pediatric Echocardiogram / ECG (starting at diagnosis / age 10).

Hip Joint Goniometric Measurement (Flexion, Extension, Abduction, Rotations)
Standardized Clinical Outcome Scales & Imaging Criteria: NSAA, 6MWT, Ankle Dorsiflexion ROM (degrees), and Echocardiogram.