Osteoporosis (Low Bone Mineral Density)Bone Loss (Porous Bones) (Osteoporosis)
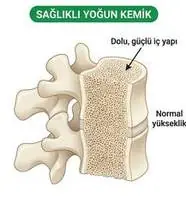
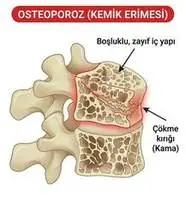
Osteoporosis (Low Bone Mineral Density) — Overview
Osteoporosis is a systemic skeletal disorder characterized by low bone mineral density (DEXA T-score ≤ -2.5 SD) and microarchitectural deterioration of trabecular and cortical bone tissue, leading to bone fragility and susceptibility to low-energy fragility fractures (vertebral compression fractures, hip fractures, and Colles wrist fractures). Rehabilitation is governed by Wolff's Law (mechanotransduction via weight-bearing and site-specific muscle pull), Sinaki's Principle (back extensor strengthening reduces vertebral fracture incidence by ~50–60%, whereas spinal flexion exercises INCREASE vertebral fractures by 300%!), and multi-component fall prevention.
Osteoporosis (bone loss / porous bones) is a condition where the inner honeycomb structure of your bones becomes thinner and less dense over time. Because bone is living tissue that responds to gentle load, weight-bearing walking, back-strengthening exercises, and balance training stimulate bone cells to stay strong while preventing falls.
Primary Causes & Biomechanics
Key Points You Should Know
- •Postmenopausal estrogen deficiency (accelerating osteoclast bone resorption), age-related osteoblast senescence, or secondary causes (chronic corticosteroid therapy, immobilization, hyperparathyroidism, vitamin D/calcium deficiency)
- •Trabecular bone plates in the vertebral bodies and femoral neck thinning faster than cortical bone
- •Thoracic kyphosis shifting the center of gravity anteriorly, combined with sarcopenia (gluteus medius/quadriceps weakness) elevating fall risk
- •The Golden Spine Rule (Sinaki's Discovery): Landmark Mayo Clinic research proved that strengthening your back extensor muscles cuts spinal fractures in half, whereas bending your spine forward (sit-ups, toe-touches) triples the risk of spinal wedge fractures! Always bend from your hips and knees with a straight back.
- •Why Swimming Alone Isn't Enough for Bone Density: While swimming is great for joints, bone cells need gravity (weight-bearing walking, stair stepping, squats, and resistance exercises) to build mineral density.
- •Preventing Falls Saves Hips: Practicing daily balance exercises and removing loose throw rugs at home is the single best defense against hip fractures.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Postural kyphosis measurement (Occiput-to-Wall distance, rib-pelvis distance <2 fingerbreadths indicates occult vertebral fracture!), height loss monitoring (>3–4 cm from young adult height), and hip/ankle ROM.
2. Special Clinical Provocation & Neurological/Functional Tests
Timed Up and Go (TUG >12s indicates high fall risk), 30-Second Chair Stand Test, Single-Leg / Tandem Stance Time, and Berg Balance Scale (BBS).
3. Standardized Clinical Outcome Scales & Imaging Criteria
Dual-Energy X-ray Absorptiometry (DEXA) of the lumbar spine (L1–L4) and femoral neck (Normal: T ≥ -1.0; Osteopenia: -1.0 to -2.5; Osteoporosis: T ≤ -2.5), and FRAX 10-year fracture probability.
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius) moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Silent Progression ('The Silent Thief'): Osteoporosis itself causes zero pain until a fragility fracture occurs.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Spinal Alignment & Safe Body Mechanics (Hip-Hinge) Phase: Strict education on avoiding spinal flexion/twisting, wall-referenced axial spinal extension, scapular retraction, and diaphragmatic/costal expansion breathing.
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius) without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in Osteoporosis.
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Sinaki Back Extensor & Weight-Bearing Osteogenic Phase: Prone active back extension (with pillow under abdomen), quadruped Bird-Dog, supine pelvic bridging, wall mini-squats, and chair sit-to-stand to apply osteogenic mechanical strain to the spine and femoral neck.
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius).
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Multi-Component Fall Prevention & Balance Phase: Supported standing hip abduction (gluteus medius), heel raises (calf raises), tandem/weight-shift balance training, brisk weight-bearing walking (30–40 min, 5 days/week), and home fall-hazard removal (removing loose rugs, adding bathroom grab bars & nightlights).
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •The Golden Spine Rule (Sinaki's Discovery): Landmark Mayo Clinic research proved that strengthening your back extensor muscles cuts spinal fractures in half, whereas bending your spine forward (sit-ups, toe-touches) triples the risk of spinal wedge fractures! Always bend from your hips and knees with a straight back.
- •Calm Protection & Gentle Start: During the initial stage of Bone Loss (Porous Bones), avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Why Swimming Alone Isn't Enough for Bone Density: While swimming is great for joints, bone cells need gravity (weight-bearing walking, stair stepping, squats, and resistance exercises) to build mineral density.
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Preventing Falls Saves Hips: Practicing daily balance exercises and removing loose throw rugs at home is the single best defense against hip fractures.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Wall-Referenced Axial Spinal Extension & Postural Decompression
1. Wall-Supported Tall Standing & Back Alignment
Standing with heels, gluteals, thoracic spine, and occiput aligned against a wall while performing axial elongation and gentle scapular/occipital pressure. Corrects thoracic hyperkyphosis and unloads anterior vertebral bodies. Specifically indicated in Osteoporosis rehabilitation to optimize trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius) biomechanics and neuromuscular control.
Stand with your heels, hips, upper back, and the back of your head lightly touching a wall. Lengthen the crown of your head toward the ceiling, gently press your shoulder blades back, and hold for 5–10 seconds while breathing calmly. Perform smoothly within a comfortable, pain-free range to support your Bone Loss (Porous Bones) recovery.
 🔍 Enlarge
2. Scapulothoracic Retraction & Depression (Middle/Lower Trapezius & Rhomboids)
2. Shoulder Blade Squeeze (Postural Alignment)
Adduction and depression of the scapulae via the middle/lower trapezius and rhomboids while inhibiting upper trapezius overactivity. Corrects anterior scapular tilt, widens the subacromial outlet, and unloads the anterior thoracic column. Specifically indicated in Osteoporosis rehabilitation to optimize trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius) biomechanics and neuromuscular control.
Sit or stand tall. Keep your shoulders relaxed away from your ears, gently draw your shoulder blades together and slightly downward toward your back pockets, hold for 5 seconds, and release. Perform smoothly within a comfortable, pain-free range to support your Bone Loss (Porous Bones) recovery.
 🔍 Enlarge
3. Supported Standing Hip Abduction & Closed-Chain Stance Stabilization
3. Counter-Supported Standing Side Leg Lift
Standing upright with light hand support, abducting the lower limb in the frontal plane while the stance-leg gluteus medius contracts isometrically to keep the pelvis level. Builds functional gait stability. Specifically indicated in Osteoporosis rehabilitation to optimize trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius) biomechanics and neuromuscular control.
Hold lightly onto a sturdy counter or chair back and stand tall. Without leaning your trunk sideways, lift your leg out to the side, pause for 2–3 seconds, and slowly return. Perform smoothly within a comfortable, pain-free range to support your Bone Loss (Porous Bones) recovery.
 🔍 Enlarge
4. Functional Closed-Kinetic-Chain Chair Transfer (Sit-to-Stand Biomechanics)
4. Controlled Chair Sit-to-Stand Transfer
Controlled transition from sitting to standing and eccentric lowering back to the chair with symmetrical weight distribution, anterior trunk inclination ('nose over toes'), and neutral frontal knee alignment. Specifically indicated in Osteoporosis rehabilitation to optimize trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius) biomechanics and neuromuscular control.
Sit near the front of a sturdy chair with your feet hip-width apart. Lean slightly forward and push evenly through both heels to stand up tall, then slowly lower yourself back down over 3 seconds. Perform smoothly within a comfortable, pain-free range to support your Bone Loss (Porous Bones) recovery.
 🔍 Enlarge
5. Quadruped Contralateral Arm-Leg Reach ('Bird-Dog' Multifidus & Deep Core)
5. All-Fours Opposite Arm & Leg Reach (Bird-Dog)
In quadruped with a neutral lumbopelvic spine and abdominal drawing-in (transversus abdominis), extending opposite upper and lower extremities horizontally without pelvic rotation or lumbar hyperextension. Minimizes spinal compressive load while maximizing multifidus recruitment. Specifically indicated in Osteoporosis rehabilitation to optimize trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius) biomechanics and neuromuscular control.
On your hands and knees, keep your back flat like a tabletop and gently tighten your tummy. Slowly reach one arm forward and the opposite leg straight back withoutarching your lower back, hold for 5 seconds, and switch sides. Perform smoothly within a comfortable, pain-free range to support your Bone Loss (Porous Bones) recovery.
 🔍 Enlarge
6. Single-Leg / Semi-Tandem Proprioceptive & Weight-Shift Balance Training
6. Supported Weight-Shifting & Tandem Balance Practice
Controlled mediolateral/anteroposterior weight shifting and tandem or single-leg stance near a stable support. Enhances mechanoreceptor feedback, ankle/hip postural reflexes, and dynamic gait stability. Specifically indicated in Osteoporosis rehabilitation to optimize trabecular and cortical skeletal bone (vertebral bodies T6–L4, femoral neck/intertrochanteric region, and distal radius) biomechanics and neuromuscular control.
Stand near a counter or sturdy chair for safety. Place one foot slightly in front of the other (or shift your weight smoothly from side to side) and hold your balance upright for 20–30 seconds. Perform smoothly within a comfortable, pain-free range to support your Bone Loss (Porous Bones) recovery.
Movements to Avoid & Strict Precautions
1. Spinal Flexion Exercises: Sit-Ups, Crunches, Toe-Touches, Rowing Machines With a Rounded Back (STRICTLY FORBIDDEN!)
1. Sit-ups, crunches, touching your toes with a rounded back, or yoga plough/forward-fold poses (STRICTLY FORBIDDEN!)
2. Bending Forward + Twisting While Lifting (Golf Ball Pick-Up, Lifting Heavy Pots/Soil Bags, Vacuuming With a Bent Back)
2. Bending at the waist and twisting while lifting heavy pots, laundry, or grandchildren
3. Walking in Slippery Socks or Keeping Loose Throw Rugs & Cluttered Cords on Floors
3. Walking in socks on slippery floors or keeping loose throw rugs in hallways
4. High-Impact Jumping or Sudden Jerking Loads on Fragile Vertebrae
4. Jumping off steps or jerky heavy lifting
Osteoporosis (Low Bone Mineral Density) — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

What Is Osteoporosis? Bone Mineral Density Grading and Fracture Prevention
Osteoporosis is a systemic skeletal disorder characterized by low bone mineral density (DEXA T-score ≤ -2.5 SD) and microarchitectural deterioration of trabecular and cortical bone tissue, leading to bone fragility and susceptibility to low-energy fragility fractures (vertebral compression fractures, hip fractures, and Colles wrist fractures). Rehabilitation is governed by Wolff's Law (mechanotransduction via weight-bearing and site-specific muscle pull), Sinaki's Principle (back extensor strengthening reduces vertebral fracture incidence by ~50–60%, whereas spinal flexion exercises INCREASE vertebral fractures by 300%!), and multi-component fall prevention.
Osteoporosis (bone loss / porous bones) is a condition where the inner honeycomb structure of your bones becomes thinner and less dense over time. Because bone is living tissue that responds to gentle load, weight-bearing walking, back-strengthening exercises, and balance training stimulate bone cells to stay strong while preventing falls.
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

Osteoporosis Exercises | 7 Strengthening Movements to Reduce Fracture Risk
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Spinal Alignment & Safe Body Mechanics (Hip-Hinge) Phase: Strict education on avoiding spinal flexion/twisting, wall-referenced axial spinal extension, scapular retraction, and diaphragmatic/costal expansion breathing.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: The Golden Spine Rule (Sinaki's Discovery): Landmark Mayo Clinic research proved that strengthening your back extensor muscles cuts spinal fractures in half, whereas bending your spine forward (sit-ups, toe-touches) triples the risk of spinal wedge fractures! Always bend from your hips and knees with a straight back.

Safe Posture, Balance, and Weight-Bearing Bone Exercises for Osteoporosis
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Sinaki Back Extensor & Weight-Bearing Osteogenic Phase: Prone active back extension (with pillow under abdomen), quadruped Bird-Dog, supine pelvic bridging, wall mini-squats, and chair sit-to-stand to apply osteogenic mechanical strain to the spine and femoral neck.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Why Swimming Alone Isn't Enough for Bone Density: While swimming is great for joints, bone cells need gravity (weight-bearing walking, stair stepping, squats, and resistance exercises) to build mineral density.

Back Extensor Strengthening and Kyphosis-Prevention Exercises in Osteoporosis
Phase 3: Functional Integration, Proprioception & Long-Term Prevention: Phase 3 Functional Integration & Long-Term Prevention: Multi-Component Fall Prevention & Balance Phase: Supported standing hip abduction (gluteus medius), heel raises (calf raises), tandem/weight-shift balance training, brisk weight-bearing walking (30–40 min, 5 days/week), and home fall-hazard removal (removing loose rugs, adding bathroom grab bars & nightlights).
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence: Preventing Falls Saves Hips: Practicing daily balance exercises and removing loose throw rugs at home is the single best defense against hip fractures.
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

Vertebral Column (Cervical & Thoracolumbar Spine) Goniometric and Tape Measurement
Goniometric ROM & Postural / Kinematic Analysis: Postural kyphosis measurement (Occiput-to-Wall distance, rib-pelvis distance <2 fingerbreadths indicates occult vertebral fracture!), height loss monitoring (>3–4 cm from young adult height), and hip/ankle ROM.

Berg Balance Scale (BBS) — Clinical Postural Control and Balance Examination
Special Clinical Provocation & Neurological/Functional Tests: Timed Up and Go (TUG >12s indicates high fall risk), 30-Second Chair Stand Test, Single-Leg / Tandem Stance Time, and Berg Balance Scale (BBS).