Lumbar Spinal Stenosis (Neurogenic Claudication)Narrowing of the Lower Back Spinal Canal (Lumbar Spinal Stenosis)
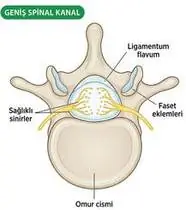
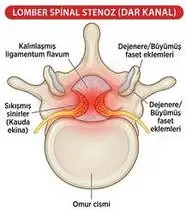
Lumbar Spinal Stenosis (Neurogenic Claudication) — Overview
Lumbar spinal stenosis is a structural narrowing of the central spinal canal, lateral recess, or neural foramina caused by the degenerative triad of disc bulging, facet joint hypertrophy/osteophytes, and buckling/thickening of the ligamentum flavum. Crucially, lumbar extension narrows the spinal canal cross-sectional area by 15–20%, whereas lumbar flexion widens the canal and foramina.
Lumbar spinal stenosis (narrowing of the lower back spinal canal) is a gradual narrowing of the bony tunnel carrying the nerves to your legs. Because standing straight pinches the tunnel and leaning slightly forward opens it up, walking causes leg heaviness that quickly fades when you sit down or lean on a shopping cart.
Primary Causes & Biomechanics
Key Points You Should Know
- •Degenerative triad: intervertebral disc height loss + facet joint osteoarthritic hypertrophy + ligamentum flavum thickening
- •Dynamic posture dependency: upright walking/extension compresses the cauda equina venous plexus and nerve roots (Neurogenic Claudication), while sitting/bending forward relieves compression (Shopping Cart Sign)
- •Hip flexor (iliopsoas) tightness pulling the lumbar spine into hyperlordosis during standing and walking
- •The Shopping Cart Clue: If you can walk much further when leaning slightly forward on a shopping cart or bicycle than when walking tall, that is the classic sign of spinal stenosis!
- •Pelvic Tilt Opens the Tunnel: Flattening your excessive lower back arch (posterior pelvic tilt) physically widens the nerve space in your spine.
- •Stationary Bike Advantage: Even when walking 200 meters feels tiring, riding a stationary bike is usually comfortable and builds leg stamina.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Lumbar flexion vs. extension symptom response, Two-Stage Treadmill Test, and hip extension ROM (Thomas test).
2. Special Clinical Provocation & Neurological/Functional Tests
Clinical differentiation of Neurogenic Claudication (relieved by sitting/bending forward, uphill walking/cycling well tolerated, pedal pulses intact) vs. Vascular Claudication (relieved by standing still, pulses diminished).
3. Standardized Clinical Outcome Scales & Imaging Criteria
Oswestry Disability Index (ODI), Swiss Spinal Stenosis Questionnaire, 6-Minute Walk Test, and lumbar MRI.
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5) moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Neurogenic Claudication: Bilateral (or unilateral) buttock, thigh, and calf cramping, heaviness, aching, and numbness triggered by standing upright and walking (especially downhill), and relieved within minutes by sitting down or leaning forward.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Flexion-Biased Canal Decompression Phase (Weeks 1–2): Williams Flexion Protocol—supine posterior pelvic tilts, single/double knee-to-chest stretches, and unloaded supine heel slides to widen the central canal and intervertebral foramina.
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5) without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in Lumbar Spinal Stenosis.
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Core Stabilization in Flattened Lordosis Phase (Weeks 2–6): Supine pelvic bridging (maintaining posterior pelvic tilt without hyperextending!), quadruped Bird-Dog, and iliopsoas hip flexor stretching (reducing anterior pelvic tilt during gait).
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5).
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Flexed-Posture Aerobic Conditioning & Gait Phase (Week 6+): Stationary cycling (slight forward trunk lean allows 30–40 min of pain-free cardio!), aquatic walking, and chair sit-to-stand.
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •The Shopping Cart Clue: If you can walk much further when leaning slightly forward on a shopping cart or bicycle than when walking tall, that is the classic sign of spinal stenosis!
- •Calm Protection & Gentle Start: During the initial stage of Narrowing of the Lower Back Spinal Canal, avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Pelvic Tilt Opens the Tunnel: Flattening your excessive lower back arch (posterior pelvic tilt) physically widens the nerve space in your spine.
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Stationary Bike Advantage: Even when walking 200 meters feels tiring, riding a stationary bike is usually comfortable and builds leg stamina.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Supine Active-Assisted Heel Slide & Synovial Diffusion Mobilization
1. Supine Heel Slide (Gentle Knee & Hip Bending)
Controlled flexion and extension of the lower extremity by sliding the heel along the support surface without axial weight-bearing. Stimulates synovial fluid diffusion across avascular cartilage and prevents capsular adhesions. Specifically indicated in Lumbar Spinal Stenosis rehabilitation to optimize central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5) biomechanics and neuromuscular control.
While lying on your back, slowly slide your heel along the bed sheet toward your hip within a comfortable, pain-free angle, hold for 3 seconds, and gently slide it back out straight. Perform smoothly within a comfortable, pain-free range to support your Narrowing of the Lower Back Spinal Canal recovery.
 🔍 Enlarge
2. Side-Lying Hip Abduction (Gluteus Medius & Frontal Plane Control)
2. Side-Lying Leg Lift (Outer Hip Strengthening)
Isolated strengthening of the gluteus medius in slight hip extension and neutral rotation. Prevents contralateral pelvic drop (Trendelenburg) and reduces dynamic knee valgus and medial compartment adduction moments. Specifically indicated in Lumbar Spinal Stenosis rehabilitation to optimize central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5) biomechanics and neuromuscular control.
Lie on your side with your bottom leg slightly bent for balance. Keep your top leg straight and slightly back, lift it up toward the ceiling without rolling your pelvis backward, hold for 3 seconds, and lower slowly. Perform smoothly within a comfortable, pain-free range to support your Narrowing of the Lower Back Spinal Canal recovery.
 🔍 Enlarge
3. Quadruped Contralateral Arm-Leg Reach ('Bird-Dog' Multifidus & Deep Core)
3. All-Fours Opposite Arm & Leg Reach (Bird-Dog)
In quadruped with a neutral lumbopelvic spine and abdominal drawing-in (transversus abdominis), extending opposite upper and lower extremities horizontally without pelvic rotation or lumbar hyperextension. Minimizes spinal compressive load while maximizing multifidus recruitment. Specifically indicated in Lumbar Spinal Stenosis rehabilitation to optimize central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5) biomechanics and neuromuscular control.
On your hands and knees, keep your back flat like a tabletop and gently tighten your tummy. Slowly reach one arm forward and the opposite leg straight back withoutarching your lower back, hold for 5 seconds, and switch sides. Perform smoothly within a comfortable, pain-free range to support your Narrowing of the Lower Back Spinal Canal recovery.
 🔍 Enlarge
4. Functional Closed-Kinetic-Chain Chair Transfer (Sit-to-Stand Biomechanics)
4. Controlled Chair Sit-to-Stand Transfer
Controlled transition from sitting to standing and eccentric lowering back to the chair with symmetrical weight distribution, anterior trunk inclination ('nose over toes'), and neutral frontal knee alignment. Specifically indicated in Lumbar Spinal Stenosis rehabilitation to optimize central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5) biomechanics and neuromuscular control.
Sit near the front of a sturdy chair with your feet hip-width apart. Lean slightly forward and push evenly through both heels to stand up tall, then slowly lower yourself back down over 3 seconds. Perform smoothly within a comfortable, pain-free range to support your Narrowing of the Lower Back Spinal Canal recovery.
 🔍 Enlarge
5. Supine Posterior Pelvic Tilt & Transversus Abdominis Activation (Abdominal Hollowing)
5. Supine Lower Back Flatten (Pelvic Tilt & Deep Core)
In hook-lying, gently drawing the umbilicus inward-upward (transversus abdominis) while tilting the pelvis posteriorly to flatten excessive lumbar lordosis against the mat. Decompresses posterior facet joints and narrows the intervertebral shear vector. Specifically indicated in Lumbar Spinal Stenosis rehabilitation to optimize central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5) biomechanics and neuromuscular control.
Lie on your back with your knees bent. Without holding your breath, gently draw your belly button inward and press the small of your back flat against the bed, hold for 5 seconds, and relax. Perform smoothly within a comfortable, pain-free range to support your Narrowing of the Lower Back Spinal Canal recovery.
 🔍 Enlarge
6. Long-Sitting Towel-Assisted Gastrocnemius-Soleus & Plantar Fascia Stretch
6. Seated Towel Calf & Foot Arch Stretch
Long-sitting with a towel looped around the metatarsal heads, applying a slow, sustained passive pull into ankle dorsiflexion. Restores gastrocnemius-soleus-Achilles length and reduces plantar fascial and equine tension. Specifically indicated in Lumbar Spinal Stenosis rehabilitation to optimize central lumbar spinal canal, lateral recess, and intervertebral foramina (L3–L5) biomechanics and neuromuscular control.
Sit with your leg extended and loop a towel around the ball of your foot. Gently pull both ends of the towel toward you until you feel a comfortable stretch in your calf and sole, holding for 20–30 seconds. Perform smoothly within a comfortable, pain-free range to support your Narrowing of the Lower Back Spinal Canal recovery.
Movements to Avoid & Strict Precautions
1. Lumbar Hyperextension Exercises (Cobra / Prone Press-Ups Are Contraindicated!)
1. Doing cobra press-ups or arching your lower back backward (pinches the narrow canal!)
2. Walking Downhill or Standing Upright in One Spot for Long Periods
2. Standing still for long periods with a swayed back or walking down steep hills without breaks
3. Sleeping Flat on Your Stomach (Forces the Lumbar Canal Into Extension)
3. Sleeping on your stomach (sleep on your side with knees slightly bent or on your back with a pillow under knees)
4. Carrying Heavy Loads That Pull the Trunk Into Lordosis
4. Carrying heavy objects in front of your body that make your lower back arch
Lumbar Spinal Stenosis (Neurogenic Claudication) — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

Clinical Differential Diagnosis of Lumbar Spondylosis, Spinal Stenosis, and Spondylolisthesis
Lumbar spinal stenosis is a structural narrowing of the central spinal canal, lateral recess, or neural foramina caused by the degenerative triad of disc bulging, facet joint hypertrophy/osteophytes, and buckling/thickening of the ligamentum flavum. Crucially, lumbar extension narrows the spinal canal cross-sectional area by 15–20%, whereas lumbar flexion widens the canal and foramina.
Lumbar spinal stenosis (narrowing of the lower back spinal canal) is a gradual narrowing of the bony tunnel carrying the nerves to your legs. Because standing straight pinches the tunnel and leaning slightly forward opens it up, walking causes leg heaviness that quickly fades when you sit down or lean on a shopping cart.
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

What Is Lumbar Spinal Stenosis? Flexion-Based Exercise Therapy Explained
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Flexion-Biased Canal Decompression Phase (Weeks 1–2): Williams Flexion Protocol—supine posterior pelvic tilts, single/double knee-to-chest stretches, and unloaded supine heel slides to widen the central canal and intervertebral foramina.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: The Shopping Cart Clue: If you can walk much further when leaning slightly forward on a shopping cart or bicycle than when walking tall, that is the classic sign of spinal stenosis!

What Is Spondylolisthesis? Spinal Stabilization and Deep Core Routine
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Core Stabilization in Flattened Lordosis Phase (Weeks 2–6): Supine pelvic bridging (maintaining posterior pelvic tilt without hyperextending!), quadruped Bird-Dog, and iliopsoas hip flexor stretching (reducing anterior pelvic tilt during gait).
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Pelvic Tilt Opens the Tunnel: Flattening your excessive lower back arch (posterior pelvic tilt) physically widens the nerve space in your spine.
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

Lumbar Spine Range of Motion and Clinical Physical Examination
Goniometric ROM & Postural / Kinematic Analysis: Lumbar flexion vs. extension symptom response, Two-Stage Treadmill Test, and hip extension ROM (Thomas test).

Lasègue (Straight Leg Raise / SLR) Test — Sciatica and Lumbar Radiculopathy Exam
Special Clinical Provocation & Neurological/Functional Tests: Clinical differentiation of Neurogenic Claudication (relieved by sitting/bending forward, uphill walking/cycling well tolerated, pedal pulses intact) vs. Vascular Claudication (relieved by standing still, pulses diminished).