Frozen Shoulder (Adhesive Capsulitis)
Frozen Shoulder (Adhesive Capsulitis) — Overview
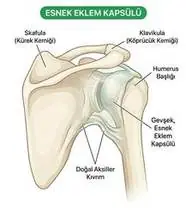
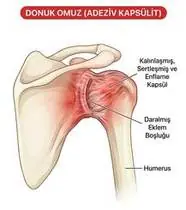
Frozen shoulder (adhesive capsulitis) is a fibroproliferative condition of the glenohumeral joint capsule and coracohumeral ligament characterized by synovial angiogenesis/inflammation followed by myofibroblastic fibrosis, capsular thickening, and obliteration of the axillary fold. It is clinically defined by equal restriction of both Active and Passive ROM in Cyriax's capsular pattern: External Rotation (most severely lost!) > Abduction > Internal Rotation.
Frozen shoulder (adhesive capsulitis) is a condition where the flexible sleeve (capsule) surrounding your shoulder joint becomes inflamed, thickened, and tight—like a shirt that has shrunk in the wash—restricting movement both when you try to lift your arm and when someone else tries to move it for you.
Primary Causes & Biomechanics
Key Points You Should Know
- •Primary idiopathic onset (strongly associated with diabetes mellitus [5x risk], thyroid disease, Dupuytren's disease, and ages 40–65) or secondary to shoulder trauma/immobilization/surgery
- •Three classical clinical stages: Stage 1 Freezing (Painful, 2–9 mos) -> Stage 2 Frozen (Stiff, 4–12 mos) -> Stage 3 Thawing (Recovery, 6–24 mos)
- •Tissue Irritability Classification (Kelley et al.): Aggressive stretching during the High-Irritability (Freezing) stage triggers an inflammatory myofibroblastic storm and worsens contracture!
- •Respecting the 3 Stages: In the early 'Freezing' stage when night pain is strong, gentle soothing pendulum movements work best—forcing hard stretches in this stage actually makes the capsule tighten more!
- •Warmth Before Stretching: In the 'Frozen' stage when pain calms down, warming the shoulder for 15 minutes before gentle wand and wall-climbing stretches helps the capsule lengthen.
- •Protecting the Arm at Night: Hugging a thick pillow under your painful arm while sleeping on your healthy side stops the capsule from pulling at night.
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Active AND Passive glenohumeral goniometry (confirming PROM = AROM restriction, with passive external rotation at the side often <10–20° and abduction <80–90°).
2. Special Clinical Provocation & Neurological/Functional Tests
Cyriax Capsular Pattern verification, Coracoid Pain Test, and normal shoulder radiographs (mandatory to rule out glenohumeral osteoarthritis or locked posterior dislocation!).
3. Standardized Clinical Outcome Scales & Imaging Criteria
SPADI, Constant-Murley Score, VAS night pain score (used to determine High vs. Moderate vs. Low tissue irritability).
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your glenohumeral joint capsule, coracohumeral ligament, and rotator interval moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Insidious, severe, diffuse shoulder ache (often waking the patient at night) followed by progressive global stiffness in all directions—especially turning the arm outward (external rotation), reaching overhead, and fastening a bra or reaching the back pocket.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Stage 1 (Freezing / High Irritability — Night Pain Predominant): NEVER force painful end-range stretching! Apply TENS/moist heat, coordinate intra-articular corticosteroid injection if indicated, and perform gentle pain-free Codman's pendulums, scapular retraction, and short-arc supine wand-assisted flexion.
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the glenohumeral joint capsule, coracohumeral ligament, and rotator interval without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in Adhesive Capsulitis.
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Stage 2 (Frozen / Moderate-to-Low Irritability — Stiffness Predominant): Moist heat before therapy, Maitland Grade III–IV inferior/posterior/anterior capsular glides, wall finger-walks (spider climb), towel-supported external rotation, and sustained low-load Total End-Range Time (TERT) stretching.
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the glenohumeral joint capsule, coracohumeral ligament, and rotator interval.
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Stage 3 (Thawing / Functional Remodeling): Full overhead wand/pulley stretches, internal rotation behind-the-back mobility, Full-Can & side-lying external rotation strengthening, and wall ball stabilization.
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •Respecting the 3 Stages: In the early 'Freezing' stage when night pain is strong, gentle soothing pendulum movements work best—forcing hard stretches in this stage actually makes the capsule tighten more!
- •Calm Protection & Gentle Start: During the initial stage of Frozen Shoulder, avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Warmth Before Stretching: In the 'Frozen' stage when pain calms down, warming the shoulder for 15 minutes before gentle wand and wall-climbing stretches helps the capsule lengthen.
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Protecting the Arm at Night: Hugging a thick pillow under your painful arm while sleeping on your healthy side stops the capsule from pulling at night.
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Codman's Pendulum Glenohumeral Decompression Exercise
1. Bent-Over Gentle Arm Pendulum Swings
Trunk flexed forward 45°–60° with the sound hand supported on a table while the affected arm hangs completely relaxed like a plumb line. Momentum from gentle trunk sway creates passive glenohumeral distraction and synovial lubrication without rotator cuff firing. Specifically indicated in Adhesive Capsulitis rehabilitation to optimize glenohumeral joint capsule, coracohumeral ligament, and rotator interval biomechanics and neuromuscular control.
Lean forward supporting your healthy hand on a table and let your affected arm hang completely relaxed toward the floor. Gently sway your body to let the arm swing in small pain-free circles without using your shoulder muscles. Perform smoothly within a comfortable, pain-free range to support your Frozen Shoulder recovery.
 🔍 Enlarge
2. Supine Wand-Assisted (Cane) Active-Assisted Shoulder Elevation
2. Lying Cane/Stick-Assisted Two-Handed Arm Raise
In supine (scapula stabilized against the plinth and gravity eliminated in the final arc), the unaffected upper extremity guides a wand/stick to elevate the affected shoulder smoothly without deltoid-induced superior humeral shear. Specifically indicated in Adhesive Capsulitis rehabilitation to optimize glenohumeral joint capsule, coracohumeral ligament, and rotator interval biomechanics and neuromuscular control.
Lie on your back holding a light stick or cane with both hands. Use your healthy arm to gently guide both arms up overhead as far as comfortable, hold for 3 seconds, and slowly lower. Perform smoothly within a comfortable, pain-free range to support your Frozen Shoulder recovery.
 🔍 Enlarge
3. Graduated Wall Finger-Walk (Spider Climb) Active-Assisted Elevation
3. Wall Finger-Climbing (Spider Walk) Exercise
Facing or standing perpendicular to a wall, walking the fingers progressively upward to achieve controlled active-assisted glenohumeral flexion/scaption while avoiding compensatory trunk lean or shoulder shrugging. Specifically indicated in Adhesive Capsulitis rehabilitation to optimize glenohumeral joint capsule, coracohumeral ligament, and rotator interval biomechanics and neuromuscular control.
Stand facing a wall and gently walk your fingers up the wall like a spider as high as you comfortably can without shrugging your shoulder, hold for 5 seconds, and walk your fingers back down. Perform smoothly within a comfortable, pain-free range to support your Frozen Shoulder recovery.
 🔍 Enlarge
4. Towel-Supported Glenohumeral External Rotation (Infraspinatus & Teres Minor)
4. Outward Forearm Rotation with Rolled Towel Under Elbow
External rotation performed at 90° elbow flexion with a rolled towel placed between the elbow and trunk (20°–30° scaption). Enhances infraspinatus/teres minor recruitment while preventing superior humeral head migration and deltoid shear. Specifically indicated in Adhesive Capsulitis rehabilitation to optimize glenohumeral joint capsule, coracohumeral ligament, and rotator interval biomechanics and neuromuscular control.
Place a small rolled towel between your elbow and your side with your elbow bent at 90 degrees. Keeping your elbow pressed gently against the towel, rotate your forearm outward, hold for 3 seconds, and return slowly. Perform smoothly within a comfortable, pain-free range to support your Frozen Shoulder recovery.
 🔍 Enlarge
5. Scapulothoracic Retraction & Depression (Middle/Lower Trapezius & Rhomboids)
5. Shoulder Blade Squeeze (Postural Alignment)
Adduction and depression of the scapulae via the middle/lower trapezius and rhomboids while inhibiting upper trapezius overactivity. Corrects anterior scapular tilt, widens the subacromial outlet, and unloads the anterior thoracic column. Specifically indicated in Adhesive Capsulitis rehabilitation to optimize glenohumeral joint capsule, coracohumeral ligament, and rotator interval biomechanics and neuromuscular control.
Sit or stand tall. Keep your shoulders relaxed away from your ears, gently draw your shoulder blades together and slightly downward toward your back pockets, hold for 5 seconds, and release. Perform smoothly within a comfortable, pain-free range to support your Frozen Shoulder recovery.
 🔍 Enlarge
6. Closed-Chain Wall Ball Stabilization & Serratus Anterior Protraction
6. Wall Ball Circles & Shoulder Blade Control
Rhythmic stabilization and small circular perturbations with the hand pressing a soft ball against the wall at shoulder height. Stimulates glenohumeral joint mechanoreceptors, serratus anterior upward rotation, and rotator cuff co-contraction. Specifically indicated in Adhesive Capsulitis rehabilitation to optimize glenohumeral joint capsule, coracohumeral ligament, and rotator interval biomechanics and neuromuscular control.
Hold a small soft ball against the wall at chest or shoulder height with your elbow nearly straight. Gently press into the ball and trace small, controlled clockwise and counterclockwise circles. Perform smoothly within a comfortable, pain-free range to support your Frozen Shoulder recovery.
Movements to Avoid & Strict Precautions
1. Aggressive, Painful Wrenching or Forced Stretching During Stage 1 (Freezing Stage)
1. Forcing your shoulder past sharp pain or letting anyone forcefully yank a painfully inflamed frozen shoulder
2. Sudden Jerking Movements (e.g., Holding a Dog Leash With the Affected Arm)
2. Holding a pulling dog leash or catching heavy falling objects with the affected arm
3. Sleeping Directly on the Affected Shoulder
3. Sleeping on the painful shoulder
4. Total Immobilization in a Sling (Accelerates Capsular Shrinkage!)
4. Keeping your arm immobilized in a sling all day
Frozen Shoulder (Adhesive Capsulitis) — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

What Is Frozen Shoulder (Adhesive Capsulitis)? Clinical Stages and Treatment
Frozen shoulder (adhesive capsulitis) is a fibroproliferative condition of the glenohumeral joint capsule and coracohumeral ligament characterized by synovial angiogenesis/inflammation followed by myofibroblastic fibrosis, capsular thickening, and obliteration of the axillary fold. It is clinically defined by equal restriction of both Active and Passive ROM in Cyriax's capsular pattern: External Rotation (most severely lost!) > Abduction > Internal Rotation.
Frozen shoulder (adhesive capsulitis) is a condition where the flexible sleeve (capsule) surrounding your shoulder joint becomes inflamed, thickened, and tight—like a shirt that has shrunk in the wash—restricting movement both when you try to lift your arm and when someone else tries to move it for you.
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

Frozen Shoulder (Adhesive Capsulitis) Range of Motion and Capsular Stretching
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Stage 1 (Freezing / High Irritability — Night Pain Predominant): NEVER force painful end-range stretching! Apply TENS/moist heat, coordinate intra-articular corticosteroid injection if indicated, and perform gentle pain-free Codman's pendulums, scapular retraction, and short-arc supine wand-assisted flexion.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: Respecting the 3 Stages: In the early 'Freezing' stage when night pain is strong, gentle soothing pendulum movements work best—forcing hard stretches in this stage actually makes the capsule tighten more!

Exercises After Shoulder Fractures and Surgery (Pendulum Phase)
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Stage 2 (Frozen / Moderate-to-Low Irritability — Stiffness Predominant): Moist heat before therapy, Maitland Grade III–IV inferior/posterior/anterior capsular glides, wall finger-walks (spider climb), towel-supported external rotation, and sustained low-load Total End-Range Time (TERT) stretching.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Warmth Before Stretching: In the 'Frozen' stage when pain calms down, warming the shoulder for 15 minutes before gentle wand and wall-climbing stretches helps the capsule lengthen.

Progressive Rehabilitation Exercises After Shoulder Fractures and Surgery
Phase 3: Functional Integration, Proprioception & Long-Term Prevention: Phase 3 Functional Integration & Long-Term Prevention: Stage 3 (Thawing / Functional Remodeling): Full overhead wand/pulley stretches, internal rotation behind-the-back mobility, Full-Can & side-lying external rotation strengthening, and wall ball stabilization.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence: Protecting the Arm at Night: Hugging a thick pillow under your painful arm while sleeping on your healthy side stops the capsule from pulling at night.
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)
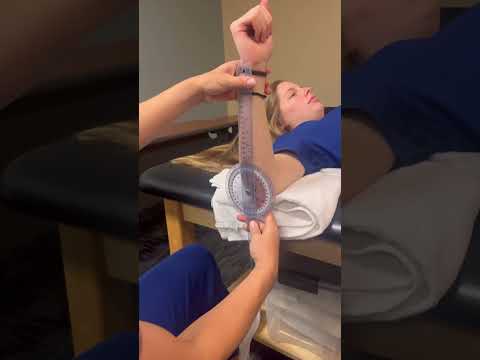
Shoulder Joint Goniometric Measurement (Flexion, Abduction, Internal & External Rotation)
Goniometric ROM & Postural / Kinematic Analysis: Active AND Passive glenohumeral goniometry (confirming PROM = AROM restriction, with passive external rotation at the side often <10–20° and abduction <80–90°).

Systematic Shoulder Joint Physical Examination and Clinical Assessment
Special Clinical Provocation & Neurological/Functional Tests: Cyriax Capsular Pattern verification, Coracoid Pain Test, and normal shoulder radiographs (mandatory to rule out glenohumeral osteoarthritis or locked posterior dislocation!).