Chronic Obstructive Pulmonary Disease (COPD)COPD / Chronic Bronchitis & Air Trapping (Chronic Obstructive Pulmonary Disease (COPD))
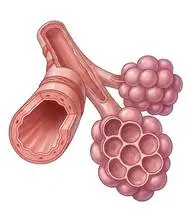
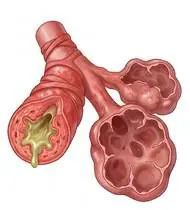
Chronic Obstructive Pulmonary Disease (COPD) — Overview
Chronic Obstructive Pulmonary Disease (COPD) is a common, preventable, and treatable chronic respiratory disease characterized by persistent, progressive, and not fully reversible expiratory airflow limitation (post-bronchodilator FEV1/FVC < 0.70) caused by chronic airway inflammation (chronic bronchitis) and alveolar parenchymal destruction with loss of elastic recoil (emphysema). During exertion, premature collapse of small airways during expiration causes Air Trapping and Dynamic Hyperinflation—which flattens the diaphragmatic dome, shortens diaphragm muscle fibers (destroying the Zone of Apposition), forces reliance on high-oxygen-cost accessory neck muscles (SCM, scalenes), and triggers severe dyspnea and peripheral quadriceps muscle dysfunction!
Chronic Obstructive Pulmonary Disease (COPD) is a long-term lung condition in which the airways narrow (chronic bronchitis) and the tiny air sacs lose their elastic spring (emphysema). The main challenge in COPD is not breathing *in*—it is that old air gets trapped inside the lungs when breathing out ('air trapping'), leaving no room for the next fresh breath! Pulmonary rehabilitation is clinically proven to be the #1 most effective treatment to reduce shortness of breath, clear mucus without exhausting coughing, and double your walking stamina.
Primary Causes & Biomechanics
Key Points You Should Know
- •Combined Chronic Bronchitis (goblet cell hyperplasia, mucus hypersecretion, ciliary loss) and Emphysema (destruction of alveolar walls reducing radial traction that holds small airways open during expiration)
- •Dynamic Hyperinflation & Flattened Diaphragm: Incomplete emptying traps air inside the lungs (elevated End-Expiratory Lung Volume), flattening the diaphragm so it can no longer act as an efficient piston
- •Systemic Skeletal Muscle Dysfunction: Chronic hypoxia, systemic inflammation, and inactivity cause Type I -> Type IIb fiber shift and quadriceps atrophy, producing early lactic acidosis that drives ventilatory demand even higher!
- •Technique #1 — Pursed-Lip Breathing (Your Built-In Airway Stent): Breathe in calmly through your nose for 2 seconds (smelling a flower), then purse your lips as if gently flickering a candle flame (never blow hard!) and breathe out slowly for 4 to 6 seconds. This gentle back-pressure keeps your tiny airways open so trapped air empties completely!
- •Technique #2 — The Forward-Lean ('Tripod') Recovery Posture: Whenever you feel breathless, DO NOT try to stand bolt upright or throw your shoulders back! Sit down (or lean against a wall/shopping cart) and lean your trunk forward resting your elbows on your knees or a table. Leaning forward pushes your diaphragm back up into a dome so breathing feels twice as easy within 30 seconds!
- •Why Strengthening Your Thighs Saves Your Breath: Strong leg muscles use 30% less oxygen to walk across a room—so leg exercises directly reduce shortness of breath!
Assessment Methods
1. Goniometric ROM & Postural / Kinematic Analysis
Spirometry & GOLD Staging (FEV1/FVC < 0.70; GOLD 1 ≥80%, GOLD 2 50–79%, GOLD 3 30–49%, GOLD 4 <30% + ABE symptom/exacerbation group), mMRC Dyspnea Scale (0–4), Modified Borg Scale (0–10), and CAT (COPD Assessment Test).
2. Special Clinical Provocation & Neurological/Functional Tests
6-Minute Walk Test (6MWT — monitoring SpO2, Heart Rate, and Borg Dyspnea/Fatigue continuously!), BODE Index (BMI, Airflow Obstruction, Dyspnea, Exercise Capacity), MIP/MEP respiratory muscle pressure, and thoracic circumference/Hoover's sign.
3. Standardized Clinical Outcome Scales & Imaging Criteria
GOLD Stage (1–4 / ABE), 6MWT distance (m), mMRC / Borg Dyspnea score, CAT score, and Pulse Oximetry (SpO2 %).
1. Range of Motion & Posture Check
Your physiotherapist gently evaluates how comfortably and smoothly your bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature moves and checks your overall posture.
2. Muscle Strength & Functional Movement Check
Your muscle balance, walking or reaching comfort, and specific gentle movement tests are evaluated without triggering sharp pain.
3. Typical Symptoms & Daily Impact Review
Progressive Exertional Dyspnea (Shortness of Breath): Breathlessness first noticed when walking uphill or climbing stairs, eventually occurring during level walking or dressing.
Treatment Options & Phase-Based Protocol
✨ Enriched GIF Exercise & Precaution GuidePhase 1: Acute Symptom Modulation, Tissue Protection & Early Activation
- •Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Pursed-Lip Breathing, Forward-Lean Relief & Airway Clearance Phase: Pursed-Lip Breathing (PLB: 2s nasal inhale -> 4–6s slow exhale through pursed lips at 1:2 / 1:3 ratio to generate 5 cmH2O intrinsic PEEP that keeps small airways open!), Forward-Lean ('Tripod') Dyspnea Relief Postures (leaning forward with elbows on knees/table pushes abdominal contents upward to restore the diaphragmatic dome!), and Active Cycle of Breathing Techniques (ACBT / Huffing).
- •Pain, Edema & Neuromuscular Modulation: Targeted physical modalities, relative load management, and early protected mobility of the bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature without provoking mechanical or inflammatory irritation.
- •Proximal & Distal Kinetic Chain Maintenance: Maintain active mobility and circulation in adjacent joints while protecting the primary healing structures in Chronic Obstructive Pulmonary Disease (COPD).
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening
- •Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Diaphragmatic Breathing, Thoracic Mobility & Inspiratory Muscle Training (IMT) Phase: Diaphragmatic & basal costal breathing (relaxing hyperactive neck/shoulder muscles via scapular relaxation), Thoracic Expansion Exercises with arm elevation, and Inspiratory Muscle Training (Threshold IMT at 30–50% MIP).
- •Biomechanical Alignment & Co-Contraction: Restore balanced agonist-antagonist force couples, joint centration, and multi-planar neuromuscular control across the bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature.
- •Myofascial Extensibility & Endurance: Address secondary compensatory tightness and build local muscular endurance within safe, symptom-free biomechanical parameters.
Phase 3: Functional Integration, Proprioception & Long-Term Prevention
- •Phase 3 Functional Integration & Long-Term Prevention: Phase 3 — Aerobic / Interval Conditioning, Quadriceps Strengthening & Energy Conservation Phase: 3–5 days/week of 20–40 min aerobic walking/cycling at 60–80% peak work or Borg Dyspnea 3–4 (using 30s work / 30s rest Interval Training in severe COPD!), lower-limb quadriceps resistance training (sit-to-stand, heel raises, knee extension—proven to reduce ventilatory demand for a given walk!), and performing all effortful ADLs during Pursed-Lip Exhalation.
- •Proprioceptive Balance & Dynamic Loading: Progress to task-specific closed-chain, balance, and functional movement patterns tailored to daily life, occupational, or athletic demands.
- •Self-Management & Relapse Prophylaxis: Establish lifelong ergonomic habits, home exercise maintenance, and early warning-sign awareness to prevent recurrence.
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion
- •Technique #1 — Pursed-Lip Breathing (Your Built-In Airway Stent): Breathe in calmly through your nose for 2 seconds (smelling a flower), then purse your lips as if gently flickering a candle flame (never blow hard!) and breathe out slowly for 4 to 6 seconds. This gentle back-pressure keeps your tiny airways open so trapped air empties completely!
- •Calm Protection & Gentle Start: During the initial stage of COPD / Chronic Bronchitis & Air Trapping, avoid painful overloading and perform the gentle, pain-free starter movements shown below to support circulation and comfort.
- •Respecting Your Body's Signals: Every movement should stay within a comfortable, non-painful zone—never force through sharp or radiating pain.
Step 2: Restoring Flexibility & Building Supporting Muscle Strength
- •Technique #2 — The Forward-Lean ('Tripod') Recovery Posture: Whenever you feel breathless, DO NOT try to stand bolt upright or throw your shoulders back! Sit down (or lean against a wall/shopping cart) and lean your trunk forward resting your elbows on your knees or a table. Leaning forward pushes your diaphragm back up into a dome so breathing feels twice as easy within 30 seconds!
- •Step-by-Step Flexibility & Support: As acute sensitivity settles, gradually build mobility and strengthen the supporting muscles around the joint at a steady, controlled pace.
- •Posture & Breathing Coordination: Keep your posture upright and breathe smoothly (never hold your breath!) during every repetition.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence
- •Why Strengthening Your Thighs Saves Your Breath: Strong leg muscles use 30% less oxygen to walk across a room—so leg exercises directly reduce shortness of breath!
- •Confident Return to Daily Life: Integrate your stronger muscles and improved balance into walking, stairs, work, and recreational activities.
- •Preventing Future Flare-Ups: Continue your core protective habits and key maintenance exercises even after symptoms resolve.
Animated (GIF) Therapeutic Exercise Guide
Animated clinical exercise protocol with biomechanical angles, target muscle groups, and dosage parameters (Click image to enlarge)
Step-by-step animated exercise demonstrations you can safely perform at home (Click image to enlarge)
 🔍 Enlarge
1. Diaphragmatic & Pursed-Lip Breathing (PLB — Autonomic & Ventilatory Control)
1. Calm Belly Breathing with Pursed-Lip Exhale
Slow nasal inhalation expanding the lower ribcage and abdomen (while relaxing accessory neck/shoulder muscles), followed by prolonged expiration through pursed lips at a 1:2 ratio. Prevents dynamic airway collapse, improves basal ventilation, and reduces sympathetic tone. Specifically indicated in Chronic Obstructive Pulmonary Disease (COPD) rehabilitation to optimize bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature biomechanics and neuromuscular control.
Sit comfortably and place one hand on your chest and the other on your belly. Breathe in slowly through your nose for 2–3 seconds so your belly gently rises, then breathe out slowly for 4–6 seconds through pursed lips as if flickering a candle. Perform smoothly within a comfortable, pain-free range to support your COPD / Chronic Bronchitis & Air Trapping recovery.
 🔍 Enlarge
2. Supine Wand-Assisted (Cane) Active-Assisted Shoulder Elevation
2. Lying Cane/Stick-Assisted Two-Handed Arm Raise
In supine (scapula stabilized against the plinth and gravity eliminated in the final arc), the unaffected upper extremity guides a wand/stick to elevate the affected shoulder smoothly without deltoid-induced superior humeral shear. Specifically indicated in Chronic Obstructive Pulmonary Disease (COPD) rehabilitation to optimize bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature biomechanics and neuromuscular control.
Lie on your back holding a light stick or cane with both hands. Use your healthy arm to gently guide both arms up overhead as far as comfortable, hold for 3 seconds, and slowly lower. Perform smoothly within a comfortable, pain-free range to support your COPD / Chronic Bronchitis & Air Trapping recovery.
 🔍 Enlarge
3. Seated Terminal Knee Extension (Open/Closed Chain VMO Focus)
3. Seated Knee Straightening & Hold
Concentric extension of the knee to the final 30°–0° terminal arc with isometric hold and ankle dorsiflexion. Restores terminal knee extension torque and stabilizes dynamic patellofemoral tracking. Specifically indicated in Chronic Obstructive Pulmonary Disease (COPD) rehabilitation to optimize bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature biomechanics and neuromuscular control.
Sit upright in a chair and slowly straighten your knee completely while pulling your toes toward you. Feel the front thigh muscle tighten, hold for 5 seconds, and slowly lower your foot. Perform smoothly within a comfortable, pain-free range to support your COPD / Chronic Bronchitis & Air Trapping recovery.
 🔍 Enlarge
4. Functional Closed-Kinetic-Chain Chair Transfer (Sit-to-Stand Biomechanics)
4. Controlled Chair Sit-to-Stand Transfer
Controlled transition from sitting to standing and eccentric lowering back to the chair with symmetrical weight distribution, anterior trunk inclination ('nose over toes'), and neutral frontal knee alignment. Specifically indicated in Chronic Obstructive Pulmonary Disease (COPD) rehabilitation to optimize bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature biomechanics and neuromuscular control.
Sit near the front of a sturdy chair with your feet hip-width apart. Lean slightly forward and push evenly through both heels to stand up tall, then slowly lower yourself back down over 3 seconds. Perform smoothly within a comfortable, pain-free range to support your COPD / Chronic Bronchitis & Air Trapping recovery.
 🔍 Enlarge
5. Thoracic Expansion Exercise (TEE) with Bilateral Arm Elevation & 3s Inspiratory Hold
5. Chest-Opening Deep Breath with Arm Raise
Synchronizing deep nasal inspiration with bilateral shoulder flexion/abduction and a 3-second end-inspiratory hold before passive/pursed-lip expiration. Opens collateral ventilation channels to prevent basal atelectasis and maintains costovertebral compliance. Specifically indicated in Chronic Obstructive Pulmonary Disease (COPD) rehabilitation to optimize bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature biomechanics and neuromuscular control.
While sitting upright, breathe in deeply through your nose while opening your arms upward and outward to expand your ribcage. Hold the breath inside for 3 seconds, then exhale slowly while lowering your arms. Perform smoothly within a comfortable, pain-free range to support your COPD / Chronic Bronchitis & Air Trapping recovery.
 🔍 Enlarge
6. Rhythmic Active Ankle Dorsiflexion & Plantarflexion Pumping (Venous/Edema Pump)
6. Ankle Toe-Pulls and Pointing (Circulation & Swelling Pump)
Rhythmic alternating contraction of the tibialis anterior and gastrocnemius-soleus complex. Activates the deep venous calf pump to prevent deep vein thrombosis (DVT), clears distal edema, and maintains talocrural mobility. Specifically indicated in Chronic Obstructive Pulmonary Disease (COPD) rehabilitation to optimize bronchial airways (chronic bronchitis), alveolar parenchyma (emphysema), and diaphragm/accessory respiratory musculature biomechanics and neuromuscular control.
While lying down or sitting with your legs supported, pull your toes and feet firmly upward toward your shins, hold for 3 seconds, then point them downward like pressing a gas pedal. Perform smoothly within a comfortable, pain-free range to support your COPD / Chronic Bronchitis & Air Trapping recovery.
Movements to Avoid & Strict Precautions
1. Holding Your Breath During Effort (Bending to Tie Shoes, Rising From a Chair, or Lifting Arms Overhead!)
1. NEVER hold your breath when bending over, standing up, or lifting your arms (ALWAYS breathe out through pursed lips during the hard part of any movement!)
2. Blowing Out Forcefully and Fast When Short of Breath (Collapses Small Airways Immediately!)
2. Forcing air out fast when breathless (causes airways to slam shut and traps more air—always exhale softly and slowly through pursed lips!)
3. Exhausting Unproductive Coughing Fits (Use 'Huffing' With an Open Glottis Instead!)
3. Barking, exhausting coughing fits (use 3 deep breaths followed by an open-mouth 'HUFF' like fogging a mirror!)
4. Avoiding Walking Out of Fear of Breathlessness (Feeds the Deconditioning Spiral!)
4. Sitting still all day out of fear of breathlessness (causes leg muscles to lose efficiency and makes breathlessness worse)
Chronic Obstructive Pulmonary Disease (COPD) — Video Guide
Click directly on any video to open and watch in a window, or review details via 📋 Summary & Options.
Condition Overview Video (1 Video)
Summary of pathophysiology, biomechanics, and clinical presentation
What the condition is, why it develops, and its basic mechanism

What Is Chronic Obstructive Pulmonary Disease (COPD) and How Is It Treated?
Chronic Obstructive Pulmonary Disease (COPD) is a common, preventable, and treatable chronic respiratory disease characterized by persistent, progressive, and not fully reversible expiratory airflow limitation (post-bronchodilator FEV1/FVC < 0.70) caused by chronic airway inflammation (chronic bronchitis) and alveolar parenchymal destruction with loss of elastic recoil (emphysema). During exertion, premature collapse of small airways during expiration causes Air Trapping and Dynamic Hyperinflation—which flattens the diaphragmatic dome, shortens diaphragm muscle fibers (destroying the Zone of Apposition), forces reliance on high-oxygen-cost accessory neck muscles (SCM, scalenes), and triggers severe dyspnea and peripheral quadriceps muscle dysfunction!
Chronic Obstructive Pulmonary Disease (COPD) is a long-term lung condition in which the airways narrow (chronic bronchitis) and the tiny air sacs lose their elastic spring (emphysema). The main challenge in COPD is not breathing *in*—it is that old air gets trapped inside the lungs when breathing out ('air trapping'), leaving no room for the next fresh breath! Pulmonary rehabilitation is clinically proven to be the #1 most effective treatment to reduce shortness of breath, clear mucus without exhausting coughing, and double your walking stamina.
Treatment and Exercise Videos
Phase-based physiotherapy protocols, mobilization, and therapeutic exercises
Step-by-step recovery and safe home exercise applications

Breathing and Thoracic Cage Exercises in COPD and Chronic Lung Diseases
Phase 1: Acute Symptom Modulation, Tissue Protection & Early Activation: Phase 1 Clinical Focus & Tissue Protection: Phase 1 — Pursed-Lip Breathing, Forward-Lean Relief & Airway Clearance Phase: Pursed-Lip Breathing (PLB: 2s nasal inhale -> 4–6s slow exhale through pursed lips at 1:2 / 1:3 ratio to generate 5 cmH2O intrinsic PEEP that keeps small airways open!), Forward-Lean ('Tripod') Dyspnea Relief Postures (leaning forward with elbows on knees/table pushes abdominal contents upward to restore the diaphragmatic dome!), and Active Cycle of Breathing Techniques (ACBT / Huffing).
Step 1: Calming Pain, Protecting the Area & Gentle Starter Motion: Technique #1 — Pursed-Lip Breathing (Your Built-In Airway Stent): Breathe in calmly through your nose for 2 seconds (smelling a flower), then purse your lips as if gently flickering a candle flame (never blow hard!) and breathe out slowly for 4 to 6 seconds. This gentle back-pressure keeps your tiny airways open so trapped air empties completely!

How to Perform Pursed-Lip Breathing (PLB) Technique
Phase 2: Progressive Mobility, Motor Control & Targeted Strengthening: Phase 2 Progressive Mobilization & Motor Control: Phase 2 — Diaphragmatic Breathing, Thoracic Mobility & Inspiratory Muscle Training (IMT) Phase: Diaphragmatic & basal costal breathing (relaxing hyperactive neck/shoulder muscles via scapular relaxation), Thoracic Expansion Exercises with arm elevation, and Inspiratory Muscle Training (Threshold IMT at 30–50% MIP).
Step 2: Restoring Flexibility & Building Supporting Muscle Strength: Technique #2 — The Forward-Lean ('Tripod') Recovery Posture: Whenever you feel breathless, DO NOT try to stand bolt upright or throw your shoulders back! Sit down (or lean against a wall/shopping cart) and lean your trunk forward resting your elbows on your knees or a table. Leaning forward pushes your diaphragm back up into a dome so breathing feels twice as easy within 30 seconds!
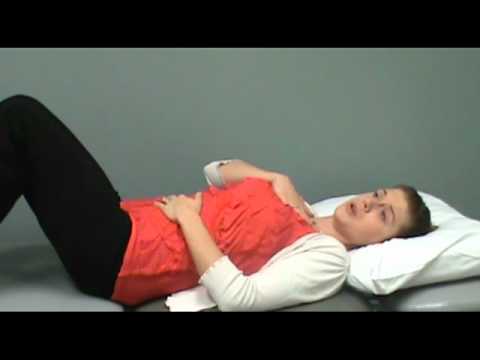
Diaphragmatic Breathing (Abdominal Breathing) Instruction and Clinical Application
Phase 3: Functional Integration, Proprioception & Long-Term Prevention: Phase 3 Functional Integration & Long-Term Prevention: Phase 3 — Aerobic / Interval Conditioning, Quadriceps Strengthening & Energy Conservation Phase: 3–5 days/week of 20–40 min aerobic walking/cycling at 60–80% peak work or Borg Dyspnea 3–4 (using 30s work / 30s rest Interval Training in severe COPD!), lower-limb quadriceps resistance training (sit-to-stand, heel raises, knee extension—proven to reduce ventilatory demand for a given walk!), and performing all effortful ADLs during Pursed-Lip Exhalation.
Step 3: Safe Daily Habits, Stamina & Preventing Recurrence: Why Strengthening Your Thighs Saves Your Breath: Strong leg muscles use 30% less oxygen to walk across a room—so leg exercises directly reduce shortness of breath!
Clinical Assessment, Goniometry & Special Test Videos
Displayed only in Healthcare Professional mode (hidden in Patient mode)

Systematic Respiratory Physical Examination (Inspection, Palpation, Percussion, Auscultation)
Goniometric ROM & Postural / Kinematic Analysis: Spirometry & GOLD Staging (FEV1/FVC < 0.70; GOLD 1 ≥80%, GOLD 2 50–79%, GOLD 3 30–49%, GOLD 4 <30% + ABE symptom/exacerbation group), mMRC Dyspnea Scale (0–4), Modified Borg Scale (0–10), and CAT (COPD Assessment Test).

Why and How Is the 6-Minute Walk Test (6MWT) Performed? Functional Capacity Assessment
Special Clinical Provocation & Neurological/Functional Tests: 6-Minute Walk Test (6MWT — monitoring SpO2, Heart Rate, and Borg Dyspnea/Fatigue continuously!), BODE Index (BMI, Airflow Obstruction, Dyspnea, Exercise Capacity), MIP/MEP respiratory muscle pressure, and thoracic circumference/Hoover's sign.